what-is-atrial-fibrillation.jpg

July 27, 2026 AbhijitHearty Life

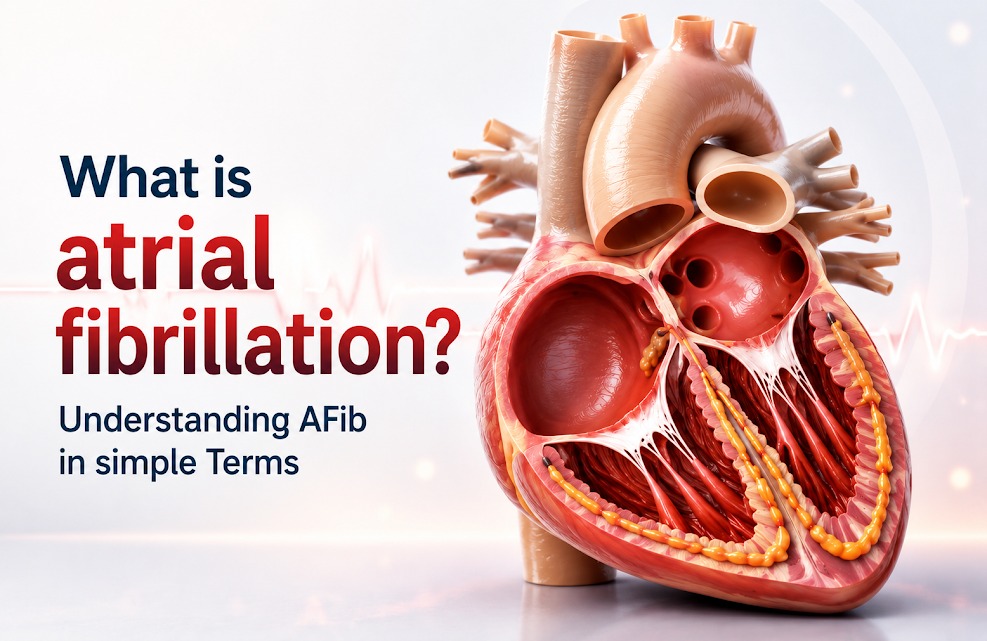
Atrial fibrillation, commonly called AFib, is becoming increasingly common among middle-aged individuals. But here’s the thing—most people don’t understand what’s actually happening inside their hearts when this occurs. You might hear the term “AFib” from your doctor, but you’re left wondering what it really means for your life, your health, and your future.

What Exactly Happens During Atrial Fibrillation?
atrial fibrillation treatment

Let me explain this simply. Your heart works like a coordinated team. It has four chambers, and they’re supposed to contract in a specific rhythm, pumping blood efficiently throughout your body. When everything works correctly, your heart beats between 60 and 100 times per minute, and each beat is regular like a drum in an orchestra.

But with atrial fibrillation, something goes wrong. The two upper chambers of your heart, called the atria, start beating chaotically. Instead of contracting in a coordinated way, they’re essentially quivering. This irregular electrical activity causes your heart to beat irregularly and often rapidly. You might feel your heart skipping beats or racing without reason.

The problem is this: when your heart isn’t pumping efficiently, it doesn’t move blood through your body the way it should. This is serious.

Also read: What is coronary angioplasty? Everything you need to know  

Why Should You Care About This?

You might think, “Okay, so my heart beats irregularly. What’s the worst that can happen?” Here’s where you need to pay attention:

Blood clots form. When blood sits in your heart chambers instead of being pumped out efficiently, it can pool and clot. These clots can travel to your brain and cause a stroke—a brain stroke that could leave you paralyzed, unable to speak, or worse.

Your heart weakens. Over time, the constant irregular beating strains your heart muscle. It’s like running a machine non-stop without proper maintenance. Eventually, it breaks down, leading to heart failure.

You feel terrible. Shortness of breath, fatigue, dizziness—these aren’t just inconveniences. They affect your quality of life, your work, and your ability to enjoy time with your family.

Other complications arise. Your risk of heart disease increases. Your blood pressure becomes difficult to control. Your overall health deteriorates.

Who Gets Atrial Fibrillation?

You might be at higher risk if you:

  • Have high blood pressure
  • Are over 65 years old (though it can happen when younger)
  • Have heart disease or a previous heart attack
  • Have thyroid problems
  • Are obese or overweight
  • Drink excessive alcohol
  • Have sleep apnea
  • Experience chronic stress
  • Have family history of AFib

If any of these apply to you, you should be paying attention to any unusual heart sensations.

Atrial Fibrillation Treatment: What Are Your Options?

The good news? Atrial fibrillation is treatable. You’re not helpless here. You have options, and finding the right approach matters tremendously.

First, there’s medication. Your doctor might prescribe medications that help regulate your heart rate or convert your heart back to a normal rhythm. Some people do very well with medication alone.

Second, there are lifestyle changes. You need to reduce stress, exercise regularly (as approved by your doctor), limit alcohol, maintain a healthy weight, and manage any underlying conditions like high blood pressure.

Third, there are medical procedures. If medication doesn’t work, procedures like ablation can be performed. An interventional cardiologist specialist trained in heart procedures can access your heart and remove the tissue causing the irregular signals. It’s minimally invasive, meaning small incisions, less pain, and faster recovery.

Finding the Right Atrial Fibrillation Doctor in Hyderabad

If you’re in Hyderabad, you’re fortunate. The city has some of India’s finest cardiac specialists. When looking for an atrial fibrillation doctor in Hyderabad, you want someone experienced, compassionate, and thorough. You want a doctor who explains things clearly, who listens to your concerns, and who works with you to create a treatment plan that fits your life.

The best atrial fibrillation doctors in India understand that AFib isn’t just a medical condition—it’s something that affects how you live. They know that you want to return to your normal activities, spend time with your loved ones, and not feel like your health is controlling your life.

Taking Action Today

Don’t wait until you have a major event to address AFib. If you experience irregular heartbeats, shortness of breath, or persistent fatigue, schedule an appointment with a cardiologist. Get evaluated. Get answers.

Your heart is the most important muscle in your body. It’s literally keeping you alive. Treating atrial fibrillation early, with the guidance of a skilled cardiologist for atrial fibrillation, can prevent serious complications like brain stroke and significantly improve your quality of life.

Also read: TAVR/TAVI Procedure in Hyderabad Minimally Invasive Care  

Moving Forward

You don’t have to live with the fear and uncertainty of AFib. Modern medicine has given us excellent tools to manage this condition. The first step is getting a proper diagnosis and treatment from qualified specialists. The second step is taking responsibility for your health—making lifestyle changes, taking medications as prescribed, and maintaining regular follow-ups with your doctor.

Ready to take control of your heart health? Dr. C. Raghu, an experienced interventional cardiologist at Yashoda Hospital, Somajiguda, Hyderabad. Your heart deserves expert care.


chronic-total-occlusion.webp

July 23, 2026 AbhijitHearty Life

Chip cto angioplasty You’ve had blockages in your arteries for a while. You’ve had procedures. You’ve taken medications. And yet your doctor just told you that you have a completely blocked artery—what’s called a chronic total occlusion. The artery isn’t just narrowed. It’s not just severely blocked. It’s completely shut off.

Your first thought is panic. But before you despair, understand this: CTO doesn’t mean you’re out of options. It doesn’t mean your case is hopeless. Modern medicine has developed specialized techniques to open even completely blocked coronaries. But you need to understand what CTO is and how it’s treated.

Understanding Coronary Artery Disease Progression

Remember how coronary artery disease develops? Plaque builds up in your arteries over time. This usually happens over years or decades.

In some people, this process is gradual. The blockage slowly increases from 50% to 75% to 90%. At each stage, blood can still squeeze through, though less efficiently.

But sometimes, the blockage continues increasing until the artery is completely sealed. No blood flows through at all. This is a chronic total occlusion—or CTO.

The word “chronic” is important. It means this blockage didn’t just happen. It’s been there for a while—usually at least three months. Your body has actually adapted somewhat, sometimes developing other small blood vessels that partially compensate for the blocked artery.

Why CTO Causes Problems

Chronic Total Occlusion Treatment

You might think, “If blood develops alternative routes, why is CTO a problem?”

Here’s why it matters:

The alternative blood vessels are limited. They don’t fully replace the original artery’s function.

Your heart remains oxygen-starved. You still experience angina (chest pain) during exertion. You still feel fatigued.

Your heart remains vulnerable. If another artery narrows, your heart has fewer reserves.

It contributes to heart failure. Prolonged oxygen deprivation weakens your heart muscle.

It increases heart attack risk. The blocked artery region is particularly vulnerable to sudden deterioration.

Also read:  Blood Clots in AFib: How They Form and Prevention 

The Challenge of Chip CTO Angioplasty Treatment

Why don’t doctors simply reopen CTOs in everyone? Because it’s technically difficult.

When an artery is completely blocked, your doctor can’t thread a wire through the blockage the way they do with partially blocked arteries. The wire hits a dead end and can’t advance.

Recanalization—opening a completely blocked artery—requires specialized expertise, specialized equipment, and particular skill. Not all interventional cardiologists perform CTO procedures. It’s a specialized subset within the specialty.

CTO Angioplasty: How It Works

If you’re a good candidate for CTO angioplasty, here’s what happens:

Step One: Imaging Your doctor performs coronary angiography to visualize the completely blocked artery. They determine the length of the blockage, its characteristics, and whether it’s a suitable target for recanalization.

Step Two: Wire Navigation This is where it gets technical. The doctor advances a guidewire toward the blockage. When the wire hits resistance, specialized techniques are used:

  • Antegrade approach: threading through from the proximal end
  • Retrograde approach: threading backwards from a collateral (alternative) vessel
  • Combination approaches: sometimes both directions are attempted

Step Three: Channel Creation Using controlled force and specialized tools, a pathway is created through the blockage. Various devices might be used—rotating burrs (chip CTO angioplasty), laser devices, or mechanical tools.

Step Four: Balloon Dilation Once a pathway is established, balloons are advanced and inflated to widen the channel.

Step Five: Stent Placement A stent—usually a coronary stent with drug-eluting properties—is placed to maintain the opening and prevent restenosis.

The Technical Complexity

CTO recanalization requires:

  • Specialized training (often fellowship training beyond standard cardiology)
  • Specialized equipment (multiple types of wires, catheters, and devices)
  • Extended procedure time (CTOs often take 2-4 hours)
  • Patience and problem-solving skills
  • Access to backup surgical support if something goes wrong

This is why CTO angioplasty is performed by a limited number of specialists, often at major cardiac centers.

When CTO Treatment is Recommended

Your coronary artery disease doctor might recommend recanalization if:

  • You have symptoms—angina, shortness of breath, exercise limitation
  • The blocked artery supplies significant heart muscle
  • You’re otherwise a good candidate
  • You’re willing to undergo the specialized procedure

Some CTOs are left alone. If you have good alternative blood supply and minimal symptoms, your doctor might say observation is appropriate. But if you’re symptomatic or at high risk, recanalization should be discussed.

Success Rates and Outcomes

Modern CTO recanalization is quite successful. Success rates typically range from 70-90% at experienced centers, depending on the complexity of the blockage.

When successful:

  • Symptoms improve dramatically
  • Exercise tolerance increases
  • Quality of life improves significantly
  • Your heart’s function often improves
  • Your long-term prognosis improves

The Different CTO Techniques

Antegrade Approach Your doctor works from the proximal (near your heart) end of the blockage, advancing a wire and devices distally (away from your heart).

Retrograde Approach Your doctor uses collateral vessels—alternative blood vessels—to approach the blockage from the distal end, working backwards toward your heart.

Hybrid Approach Your doctor switches between antegrade and retrograde techniques, using whichever works best as the procedure progresses.

Specialized Procedures For particularly challenging blockages, specialized techniques like chip angioplasty (rotational atherectomy) might be employed. These techniques use rotating burrs or lasers to grind away hardened plaque.

Finding a CTO Specialist

Not every coronary artery disease specialist performs CTO recanalization. You need someone with specific expertise.

The best angioplasty expert in India who handles CTOs will have:

  • Dedicated CTO training
  • High success rates (preferably >80%)
  • Low complication rates
  • Extensive experience (hundreds of CTO procedures)
  • Access to all necessary equipment
  • Support from surgical backup
  • Genuine expertise and not just willingness to try

In Hyderabad, a few centers have true CTO expertise. Ensure your angioplasty expert in Hyderabad has specific CTO experience.

Risks and Complications

CTO procedures do carry risks:

  • Perforation of the artery (usually manageable)
  • Contrast-induced kidney injury
  • Stroke (rare)
  • Heart attack during procedure
  • Access site bleeding
  • Unsuccessful recanalization (wire can’t get through despite attempts)

At specialized centers with experienced operators, major complications are rare (2-5%).

Life After CTO Recanalization

If your CTO is successfully recanalized:

  • You’ll feel better relatively quickly
  • Medications will be adjusted
  • A stent is now in place, requiring antiplatelet therapy
  • Regular follow-ups ensure your stent is functioning well
  • Your heart function may improve over weeks to months

Most people experience significant quality of life improvement.

If Recanalization Isn’t Possible

Sometimes, despite best efforts, the wire can’t traverse a CTO. In this case:

  • Your doctor will stop and not force the issue
  • You’ll continue medical management
  • Other treatments might be considered—medication optimization, other interventions if different arteries are treatable
  • You’ll need close follow-up

This isn’t failure. CTO anatomy varies, and some blockages are simply too difficult. Your doctor’s decision to stop is actually protecting you.

Prevention and Management

Going forward, focus on:

  • Medications—take them exactly as prescribed
  • Lifestyle changes—diet, exercise, stress management
  • Smoking cessation if applicable
  • Managing diabetes and hypertension
  • Regular follow-ups and testing
  • Addressing other coronary blockages

Your Path Forward

Chronic total occlusion sounds intimidating. But with modern techniques and experienced specialists, CTOs are increasingly manageable. Many people who thought their blockage couldn’t be opened are now living symptom-free lives after successful CTO recanalization.

The key is finding a coronary artery disease doctor with genuine CTO expertise and being realistic about what’s possible.

Also read: What is coronary angioplasty? Everything you need to know
Also read: CHIP Angioplasty: Advanced Coronary Artery Disease Treatment Explained 


If you have a chronic total occlusion or complex coronary disease, expert care makes a difference. Consult with Dr. C. Raghu, an interventional cardiologist with expertise in complex coronary interventions.


Blood-cloth-afib.png

July 21, 2026 AbhijitHearty Life

Blood Clots in AFib You don’t think about your blood clotting. You just assume it works the way nature intended. But what if I told you that your irregular heartbeat is creating the perfect environment for dangerous blood clots to form inside your heart? What if one of these clots breaks loose and travels to your brain, causing a stroke that changes your life forever?

This isn’t fear-mongering. This is reality for people with atrial fibrillation treatment. Blood clots in AFib represent one of the most serious complications of an irregular heartbeat, and understanding how they form is the first step to protecting yourself.

How Your Blood Clots in AFib Normally
Blood Clots in AFib

Your body is incredibly intelligent. When you cut yourself, your blood clots to stop the bleeding. Platelets rush to the scene, and proteins in your blood create a mesh that seals the wound. This is a life-saving mechanism.

But blood clotting only works well when blood is flowing smoothly. Your heart pumps blood like a continuous wave through your arteries and veins. The constant movement keeps blood from sitting in one place long enough to clot unnecessarily.

When you have AFib, this smooth flow stops.

The AFib Problem: Stagnant Blood

Remember what happens during AFib? Your atria aren’t contracting properly. They’re quivering instead of pumping. Blood doesn’t move out of these chambers as it should. Instead, it sits there. It pools. It stagnates.

Think of it like a river. When water flows, it stays clean and fresh. When water sits in a pond, things start to grow and accumulate. Your blood is similar.

When blood stagnates in your heart’s atria for extended periods, it naturally starts to clot. Your body doesn’t know this is abnormal—it just thinks blood is sitting still and needs protection. So it activates the clotting mechanism.

Where Do These Clots Go?

Here’s what terrifies people, and rightfully so. A clot can

  • Stay in your heart and grow larger
  • Break loose and travel through your bloodstream
  • Reach your brain and block blood flow, causing a brain stroke
  • Block other arteries in your body, causing problems elsewhere
  • Damage your heart further


A stroke from AFib-related blood clots is particularly serious. These strokes tend to be more severe than other types of strokes. They cause more disability and more death.

Who’s Most at Risk?

Your risk of developing blood clots from AFib increases based on several factors:

Age matters. People over 65 face higher risk.

Duration counts. If you’ve had AFib for years, clot risk increases.

Your other health conditions matter. High blood pressure, diabetes, heart failure, previous stroke—these all increase your risk.

Your heart function matters. If your heart is weakened, blood pools more easily.

Prevention: Your Most Important Tool

Here’s the empowering part: you can prevent AFib blood clots. You have real options.

Blood Thinning Medications

Your doctor will likely recommend anticoagulants—medications that thin your blood and prevent clotting. These are lifesavers for AFib patients.

Warfarin is the traditional choice. It’s effective but requires regular blood tests and diet consistency.

Newer options like apixaban, rivaroxaban, dabigatran, and edoxaban work differently. They’re often more convenient with fewer dietary restrictions.

Your heart specialist in Hyderabad will help you choose the right medication based on your specific risk factors and medical history.

Atrial Fibrillation Treatment Matters

The type of atrial fibrillation treatment you receive affects clot risk. Ablation procedures, performed by skilled interventional cardiologists, can sometimes eliminate AFib entirely, reducing or eliminating the need for blood thinners in some cases.

Lifestyle Modifications

You control many factors:

  • Control your blood pressure through medication and lifestyle
  • Manage diabetes if you have it
  • Stop smoking immediately
  • Limit alcohol significantly
  • Exercise regularly as approved by your doctor
  • Maintain a healthy weight
  • Reduce stress through meditation, yoga, or counseling
  • Stay hydrated properly
  • Sleep adequately


What Happens During Atrial Fibrillation Treatment?

When you work with a specialized atrial fibrillation doctor in Hyderabad or any of the best atrial fibrillation doctors in India, they don’t just treat the irregular heartbeat. They treat the whole picture, including clot prevention.

Your doctor will assess your clot risk using standardized scoring systems. Based on this assessment, they’ll recommend appropriate anticoagulation therapy.

If you undergo procedures like catheter ablation or other interventions, your specialist will guide you on blood thinner use before and after procedures.

Also read: What is a pulmonary embolism? Life-Threatening Clot Explain  

For Atrial Flutter Treatment

Similar principles apply to atrial flutter treatment. Though flutter is slightly different from AFib, it still carries stroke risk if persistent, and anticoagulation may be necessary.

Finding Your Specialist

You need someone who understands both AFib and the serious complication of blood clots. You need the best cardiologist for AFib who takes clot prevention as seriously as treating the irregular heartbeat itself.

In Hyderabad, you have access to excellent specialists. The atrial fibrillation doctors in India at major hospitals bring world-class expertise to your care.

Don’t Ignore Warning Signs

If you have AFib or are at risk for it, watch for:

  • Sudden weakness on one side of your body
  • Facial drooping
  • Speech difficulties
  • Sudden severe headache
  • Chest pain
  • Severe shortness of breath
  • Loss of consciousness


These could indicate a brain stroke from an AFib-related clot. Seek emergency care immediately.


Also read: What is coronary angioplasty? Everything you need to know  

Your Path Forward

Living with AFib doesn’t mean living in fear of blood clots. It means taking preventive action. It means taking your medications as prescribed. It means maintaining regular check-ups. It means making the lifestyle changes that support your heart health.

You have more control than you might think. Work closely with qualified specialists, follow their guidance, and take your health seriously.

Don’t leave your heart health to chance. Schedule a consultation with Dr. C. Raghu, an interventional cardiologist specializing in AFib and stroke prevention.


what-is-a-pulmonary-embolism.jpg

July 13, 2026 AbhijitHearty Life

Pulmonary embolism You’re sitting at work when suddenly you can’t catch your breath. Your chest feels tight. Your heart is racing. You feel like you’re going to pass out. You’re scared genuinely terrified.

Your coworker calls an ambulance. At the hospital, after tests, the doctor tells you, “You have a pulmonary embolism.” A blood clot has traveled to your lungs.

Your world stops. You’ve heard that phrase before “pulmonary embolism” and you know it’s serious. You need to understand what just happened, why it happened, and what comes next.

What Exactly Is a Pulmonary Embolism?

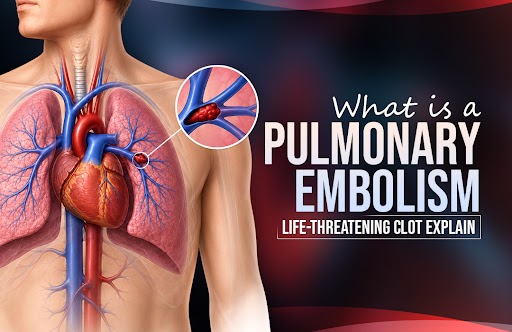
A pulmonary embolism—often called PE—occurs when a blood clot travels through your veins and lodges in the blood vessels of your lungs. This clot blocks blood flow, preventing oxygen from being transferred to your blood.

The clot usually starts in your legs or pelvis. It breaks loose and travels through your venous system, through your right heart, and into your lungs, where it gets stuck—too large to fit through the narrowing vessels.

Think of it like this: imagine a road with traffic flowing normally. Suddenly, a large object blocks the road. Traffic backs up. Things are chaos.That’s what happens in your lungs when a clot blocks blood flow.

Also read: DVT to Pulmonary Embolism: The Risks and Prevention  

Why You Get Blood Clots: Risk Factors

Several situations increase your clot risk:

Immobility: Sitting for long periods—long flights, road trips, bed rest after surgery, and office work. When you don’t move, blood pools in your legs instead of circulating normally. Pooled blood clots.

Surgery: After surgery, blood clotting mechanisms activate. You’re immobile during recovery. You have trauma to your tissues. This combination creates perfect conditions for clots.

Cancer: Cancer cells activate clotting mechanisms. Cancer patients have high PE risk.

Birth control pills or hormone therapy: Estrogen increases clotting tendency.

Pregnancy and postpartum period: Pregnancy naturally increases clotting tendency. After delivery, you’re at even higher risk.

Previous blood clots: If you’ve had one clot, you’re at higher risk for another.

Genetic clotting disorders: Some people have genetic variations making their blood clot more easily.

Obesity: Extra weight increases clot risk.

Immobilized leg: Fractures, casts, or reduced mobility in one leg increase risk.

Recent hospitalization: Being bedridden increases risk.

Smoking: Smoking damages blood vessels and increases clotting.

Heart disease: Certain heart conditions increase PE risk.

Symptoms: The Warning Signs

Pulmonary embolism symptoms vary based on the clot’s size and location. Small clots might cause mild symptoms. Large clots can cause sudden collapse.

Common symptoms include:

  • Sudden severe shortness of breath
  • Chest pain, especially when breathing deeply
  • Rapid heartbeat
  • Dizziness or lightheadedness
  • Fainting
  • Anxiety or sense of impending doom
  • Cough (sometimes with blood-tinged sputum)
  • Leg pain or swelling (if clot originated there)

Important: These symptoms warrant emergency evaluation. Don’t wait. Call 911 or go to the emergency room immediately.

Why PE is So Serious

Your lungs’ job is to oxygenate blood. A clot blocking lung blood vessels prevents oxygenation.

Your oxygen levels drop. Your brain, heart, and other organs aren’t getting sufficient oxygen.

Your right heart overworks. The right ventricle has to pump harder against the blocked vessels. It can become exhausted.

Your blood pressure drops. If the clot is large, your cardiovascular system can collapse.

You go into shock. Organ systems fail without sufficient oxygen.

This is why pulmonary embolism is a medical emergency. It can be fatal. Sudden massive PE can cause sudden death.

Diagnosis: How Doctors Identify PE

If your doctor suspects PE, several tests confirm the diagnosis:

CT Pulmonary Angiography (CTPA): This is usually the first test. A CT scanner with special imaging shows blood clots in your lungs’ vessels. It’s quick, accurate, and readily available.

D-dimer blood test: This blood test measures a substance released when clots break down. If D-dimer is normal, PE is very unlikely. If elevated, further testing is needed.

Chest X-ray: Might show pneumonia or other lung problems, but usually looks normal in PE.

Echocardiogram: Ultrasound of your heart. Shows if your right heart is strained.

Arterial blood gas: Measures oxygen and carbon dioxide levels in your blood.

Ventilation-perfusion scan: Shows areas of your lungs receiving ventilation (air) but not perfusion (blood flow). Mismatches suggest PE.

Also Read: Atrial Fibrillation treatment in India: Complete Guide 

Pulmonary Embolism Treatment: Your Options

Once PE is diagnosed, immediate treatment begins.

Anticoagulation Therapy: Blood thinners prevent clots from growing and new clots from forming. They don’t dissolve existing clots—your body does that naturally—but they prevent expansion while your body works to break down the clot.

Medications include:

  • Heparin: Given intravenously in the hospital
  • Low molecular weight heparin: Injected subcutaneously, can be outpatient
  • Warfarin: Oral blood thinner for long-term management
  • Direct oral anticoagulants: Newer medications like apixaban or rivaroxaban

Thrombolytic Therapy (Clot-Busting): For massive PEs or hemodynamically unstable patients, medications that dissolve clots might be used. These medications have risks but can be lifesaving in severe PE.

Mechanical Thrombectomy: For very large clots or patients who can’t tolerate blood thinners, a pulmonary embolism specialist might perform mechanical thrombectomy. A catheter-based device removes clot material directly.

IVC Filter: In rare cases where you can’t take blood thinners, an inferior vena cava (IVC) filter might be placed. This filter catches clots traveling from legs before they reach your lungs.

Recovery and Aftercare

After initial PE treatment:

You’ll stay in the hospital for a few days to ensure stability and adjust medications.

You’ll take blood thinners for months to years, depending on circumstances.

Regular blood tests monitor your blood’s clotting tendency.

Follow-up imaging might be done to ensure clots are resolving.

You’ll gradually resume activity as you recover.

Most people recover completely from their first PE if treated promptly.

Post-PE Complications

Some people develop complications after PE:

Post-thrombotic syndrome: Chronic leg swelling and pain from valve damage in leg veins.

Chronic thromboembolic pulmonary hypertension (CTEP): Some clots don’t fully dissolve, leading to permanent lung scarring and heart strain.

Recurrent PE: Some people have another PE despite treatment.

This is why finding the right pulmonary embolism doctor and following their guidance completely is critical.

Finding Your PE Specialist

You need a pulmonary embolism specialist in India or your local area who:

  • Understands PE completely
  • Can manage your acute care
  • Monitors for complications
  • Helps you navigate blood thinner therapy
  • Works with you long-term

A pulmonary embolism specialist in Hyderabad can provide comprehensive care if you’re in that region.

For complicated cases or patients not responding well, the best doctor for pulmonary embolism at a major medical center might be appropriate.

Prevention: Reducing Your Risk

If you’re at risk for PE:

Move regularly. On flights or road trips, get up and walk every 2 hours.

Compression socks. These prevent blood pooling in your legs during immobility.

Leg exercises. Flex your calves while sitting to activate leg muscles and promote blood flow.

Hydration. Dehydration increases clot risk. Drink plenty of water.

Blood thinner prophylaxis. If you’re having surgery or hospitalization, your doctor might prescribe preventive blood thinners.

Stop smoking. Smoking damages blood vessels.

Manage your weight. Obesity increases PE risk.

Control medical conditions. Manage heart disease, cancer risk factors, and other conditions that increase clot risk.

Life After Pulmonary Embolism

Most people recover completely from PE. You’ll likely take blood thinners for several months to several years, depending on whether this was provoked (caused by a temporary situation) or unprovoked (no clear cause).

You’ll have restrictions initially bu gradually return to normal activities.

You’ll attend follow-up appointments and take medications as prescribed.

You’ll be aware of PE symptoms and seek immediate care if symptoms recur.

Many people go on to live normal, full lives after PE. The key is treating it promptly and following your doctor’s guidance carefully.

Moving Forward

Pulmonary embolism is serious. It demands immediate medical attention. It requires ongoing management. But it’s treatable, and most people recover well.

If you’ve experienced PE or are at high risk, understand your risk factors. Modify them where possible. Know the warning signs. Seek immediate care if symptoms develop.

Work with qualified specialists. Take your medications. Attend your follow-ups. Be an active participant in your care.

Your life after PE can be full and normal. It requires attention to your health, but it’s absolutely possible.

If you’ve experienced a pulmonary embolism or are concerned about your risk, expert medical guidance is essential. Consult with Dr. C. Raghu, a cardiologist in Hyderabad specializing in cardiovascular emergencies and blood clot management.


WHAT-IS-CTEPH.webp

July 7, 2026 AbhijitHearty Life

CTEPH -You survived a blood clot in your lungs. That  pulmonary embolism was terrifying—sudden shortness of breath, chest pain, panic. You got treatment. You survived. You should be back to normal, right?

But you’re not. Months later, you’re still experiencing shortness of breath. You can’t do the activities you used to do. You get winded walking up the stairs. Your doctor is concerned and mentions something called CTEPH. You’ve never heard of it. It sounds rare and scary.

The truth is CTEPH Chronic Thromboembolic Pulmonary Hypertension—is rare. But it’s also treatable. Understanding what it is and what your options are can transform your outlook from hopelessness to hope.

Understanding Pulmonary Embolism First

Before we discuss CTEP, you need to understand how it develops.

A pulmonary embolism occurs when a blood clot travels to your lungs and blocks blood flow. This is a medical emergency. Symptoms include:

  • Sudden severe shortness of breath
  • Chest pain
  • Rapid heartbeat
  • Dizziness or fainting
  • Anxiety and sense of doom

With proper treatment—blood thinners, sometimes clot-busting medications, or mechanical thrombectomy—most people recover from acute pulmonary embolism.

But here’s what makes CTEP different: some clots don’t dissolve completely. Small clots remain trapped in your lungs’ blood vessels.

Also read: Heart Attack in Younger Lifestyle Change Not to be Ignored  

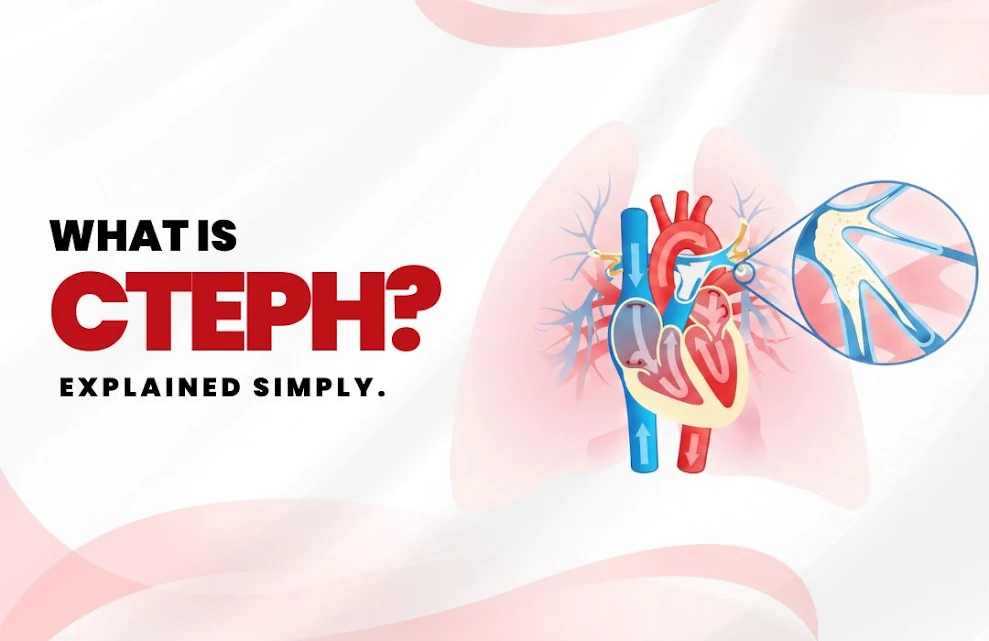
What Exactly Is CTEPH?

CTEP develops when:

  1. You have a pulmonary embolism (usually)
  2. The clot doesn’t fully dissolve despite treatment
  3. Scar tissue forms around the clot
  4. Blood vessels in your lungs narrow
  5. Your right heart has to work harder to pump blood through these narrowed vessels
  6. Over weeks to months, your lungs become permanently scarred with clot remnants

This leads to pulmonary hypertension—abnormally high blood pressure in your lung’s blood vessels. Your right heart becomes exhausted trying to pump against this resistance.

The term “chronic thromboembolic” means you have chronic (long-term) clots causing problems. “Pulmonary hypertension” means high blood pressure in your lungs. Together: CTEP.

Why CTEP is Serious

You might think, “Okay, so the clot didn’t dissolve completely. I’m on blood thinners. I should be fine.”

Unfortunately, CTEP is progressive and serious:

Your heart weakens. Your right ventricle becomes enlarged and exhausted. It’s being asked to pump harder than it can sustain long-term.

Blood backs up. Since blood can’t flow normally through your lungs, it backs up into your right heart and then into your veins. This causes swelling in your legs and abdomen.

Your oxygen levels drop. Blood flowing through scarred lung vessels can’t pick up oxygen properly. You feel constantly short of breath.

Your kidneys suffer. Poor circulation affects kidney function.

Ultimately, your heart fails. Without intervention, CTEP progresses to right heart failure—a critical condition.

This is why early diagnosis and treatment matter enormously.

Symptoms of CTEPH

CTEP develops gradually. You might have these symptoms months after your original pulmonary embolism:

  • Persistent shortness of breath
  • Fatigue—extreme, debilitating tiredness
  • Chest pain
  • Swelling in your legs (one leg or both)
  • Dizziness or fainting
  • Rapid heartbeat
  • Chest discomfort
  • Difficulty exercising

The key: these symptoms persist despite being on blood thinners. This is what separates CTEP from normal recovery from pulmonary embolism.

Diagnosis: How Doctors Identify CTEPH

If your doctor suspects CTEP, they’ll order tests:

An echocardiogram shows how your heart is functioning and estimates pressure in your lungs.

CT angiography shows lung blood vessels and can sometimes identify clot remnants.

V/Q scan (ventilation-perfusion scan) shows which parts of your lungs are getting blood flow and which aren’t. A pattern of mismatched areas—areas with ventilation but no perfusion—is classic for CTEP.

Right heart catheterization is the definitive test. A catheter is threaded through your veins to your right heart. Pressures are measured. A pulmonary hypertension in India specialist will confirm if pressures are elevated due to chronic clots.

Pulmonary Hypertension: A Spectrum Condition

Not all pulmonary hypertension is from CTEP. It’s a spectrum condition:

Group 1 Pulmonary Hypertension: Idiopathic (no known cause) or hereditary. Medications help but don’t cure.

Group 2 Pulmonary Hypertension: From left-heart disease.

Group 3 Pulmonary Hypertension: From lung disease.

Group 4 Pulmonary Hypertension: From CTEP and other thromboembolic causes. This is the group that can potentially be cured with surgery.

This distinction is crucial. CTEP can sometimes be cured. Other pulmonary hypertension types cannot—they require lifelong management.

Treatment: Pulmonary Endarterectomy—The Potential Cure

The gold-standard treatment for suitable CTEP patients is pulmonary endarterectomy. This surgery removes the chronic clots and scar tissue from inside your lung’s blood vessels.

How It Works:

Your surgeon uses cardiopulmonary bypass (heart-lung machine). Your core body temperature is lowered to near-freezing. This slows your metabolism and protects your organs.

While you’re in this protected state, the surgeon carefully removes clot material and scar tissue from inside the pulmonary arteries. The surgery requires precision and expertise.

After clot removal, your lungs can oxygenate blood normally. Your heart no longer has to work against massive resistance. Your right ventricle can recover.

The Outcome:

When successful, pulmonary endarterectomy can dramatically improve or completely reverse pulmonary hypertension. People go from being disabled to returning to normal activities. It’s truly life-changing—the closest thing we have to a cure for CTEP.

Not Everyone is a Surgical Candidate

Unfortunately, not all CTEP patients can have pulmonary endarterectomy.

Reasons include:

  • Clots are in very small peripheral vessels (inaccessible to surgery)
  • Your overall health is too poor for major surgery
  • Your right heart is too weakened
  • Associated conditions make surgery too risky

If you’re not a surgical candidate, other treatments help:

Medications for pulmonary hypertension can improve symptoms and slow progression.

Anticoagulation therapy prevents new clots.

Diuretics help manage fluid buildup.

Oxygen therapy if oxygen levels are low.

Mechanical thrombectomy is a newer, less invasive option for certain patients. Instead of open surgery, a catheter-based procedure removes clots. This isn’t suitable for all patients, but it’s an alternative for some who aren’t surgical candidates.

Finding Your CTEPH Specialist

CTEP is rare, and expertise is limited. You need a pulmonary embolism specialist with specific CTEP experience.

Ideal specialists:

  • Have training in pulmonary hypertension
  • Understand CTEP specifically
  • Have access to pulmonary endarterectomy surgeons if you’re a candidate
  • Can discuss all options—surgery, medications, mechanical thrombectomy
  • Work at major cardiac/pulmonary centers

The best cardiologist in India or a pulmonary hypertension specialist at a major center can evaluate whether you’re a candidate for specific treatments and guide your care.

Your Recovery and Prognosis

If you undergo successful pulmonary endarterectomy:

Immediate recovery: Hospital stay of several days to a week. You’ll have significant pain initially—this was major surgery. Pain control is important.

Weeks to months: Gradual improvement. Your shortness of breath decreases. Your stamina increases. You feel better each week.

Months to years: Your heart gradually recovers. Lung function normalizes. Many people return to completely normal activities.

If you’re managed medically (not surgical):

Medications help stabilize your condition and slow progression.

Your quality of life improves compared to untreated CTEP, but you won’t achieve the dramatic recovery seen after successful surgery.

Regular monitoring ensures treatments are working and complications are caught early.

Also read: DVT to Pulmonary Embolism: The Risks and Prevention 

Prevention and Risk Factors

If you’ve had a pulmonary embolism:

  • Stay on anticoagulation therapy as prescribed—don’t stop early
  • Report any persistent shortness of breath to your doctor
  • Get regular follow-ups even if you feel fine
  • Avoid immobility—move regularly, especially on long flights or road trips
  • Stay hydrated

If you have risk factors for blood clots:

  • Surgery recovery
  • Cancer
  • Pregnancy
  • Birth control pills
  • Prolonged immobility

Talk to your doctor about prevention strategies.

Moving Forward

CTEP is rare, but if you have it, your world has probably turned upside down. You went from managing a pulmonary embolism to discovering you have a chronic disease.

But here’s hope: CTEP is treatable. Some patients are cured. Others have their condition significantly improved. Your quality of life can improve substantially.

The key is finding the right pulmonary embolism specialist who understands CTEP completely and can discuss all available options—surgery, medications, and newer techniques like mechanical thrombectomy.

Don’t accept hopelessness. Seek expertise. Explore your options. Work with specialists who understand this rare condition.

If you’ve had a pulmonary embolism and are experiencing persistent symptoms, expert evaluation is critical. Dr. C. Raghu and cardiac specialists at Yashoda Hospital can help determine whether you might have CTEP and discuss your treatment options.

Visit drraghu.com to schedule a comprehensive evaluation with a heart specialist in Hyderabad.


Coronary-angioplasty-2.webp

Coronary angioplasty: Your chest feels tight. You’ve been getting shortness of breath lately, especially when you climb stairs or walk briskly. You’re worried. Your doctor has mentioned something called coronary angioplasty, but you don’t understand what it is or whether you really need it.

You’re not alone. Many middle-aged people are facing coronary artery disease without fully understanding their treatment options. The term “angioplasty” sounds intimidating. The word “stent” makes you nervous. But here’s the truth: understanding what these procedures are and how they can help you is empowering. It gives you control over your health decisions.

Understanding Coronary angioplasty Artery Disease
Coronary angioplasty

Before we discuss angioplasty, you need to understand the problem it solves.

Your heart is a muscle that needs oxygen to work. Coronary arteries deliver oxygen-rich blood to your heart. These are the highways of your cardiovascular system. Over time, for various reasons—high cholesterol, high blood pressure, smoking, diabetes, and stress—fatty deposits build up inside these arteries. This buildup is called plaque.

Coronary artery disease happens when these arteries narrow. Blood flow decreases. Your heart struggles to get enough oxygen, especially during activity or stress. You feel chest pain. You feel exhausted. You feel vulnerable.

This is serious. Completely blocked arteries lead to heart attacks.

What Exactly is Coronary Angioplasty?

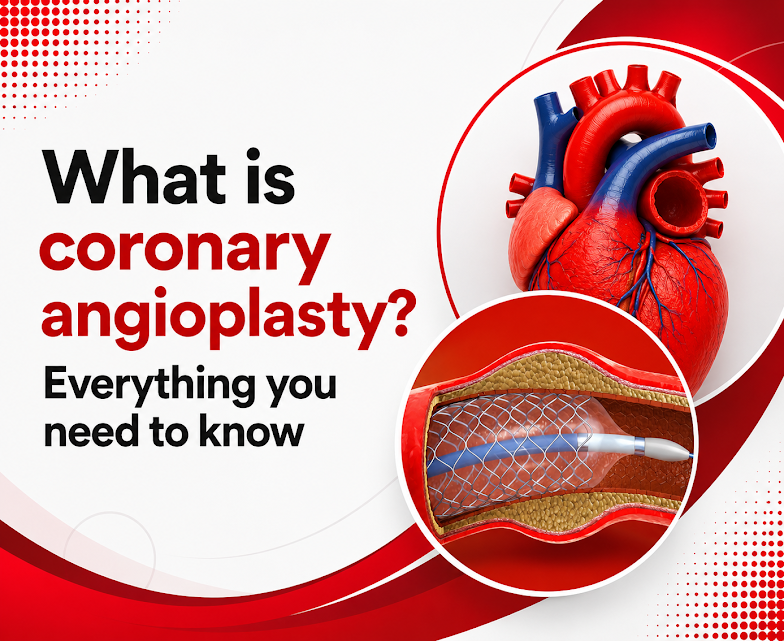
Let’s demystify this. Coronary angioplasty is a minimally invasive procedure that opens blocked or narrowed coronary arteries. It’s not surgery in the traditional sense—no large incisions, no general anesthesia, no weeks of recovery.

Here’s how it works:

Step One: Angiogram Your coronary artery disease doctor first performs an angiogram. A thin catheter (tube) is inserted through an artery in your groin or arm. This catheter is guided to your heart. A special dye is injected through the catheter, and X-rays are taken. These images show exactly where your arteries are blocked or narrowed. You’re awake during this procedure, though mildly sedated.

Step Two: Balloon Inflation Once the blocked area is identified, a balloon catheter is advanced to that location. When the catheter is in position, the balloon is inflated. This balloon pushes the plaque against the artery wall, widening the artery and restoring blood flow. You might feel slight chest discomfort—this is normal and temporary.

Step Three: Stent Placement In most modern angioplasty procedures, a stent is placed. Think of a stent as a tiny mesh tube. It keeps the artery open after the balloon is removed, preventing the artery from narrowing again. Most stents today are drug-eluting, meaning they release medication that prevents scar tissue buildup.

The entire procedure typically takes 30 minutes to an hour.

Why Your Doctor Recommends Angioplasty

Your coronary artery disease specialist recommends angioplasty for specific reasons:

  • You have significant blockages causing symptoms
  • You have blockages that could cause a heart attack
  • Medical management (medications) isn’t sufficient
  • You’ve had a recent heart attack
  • You’re having a heart attack right now

Not all coronary artery disease requires angioplasty. Some people do well with medications. But when angioplasty is appropriate, it can be life-changing.

Also read: Pulmonary Embolism in India: Emergency & Finding Specialist  

The Difference Between Angioplasty and Angiogram

Many people confuse these terms. Let me clarify:

An angiogram is a diagnostic test. It shows what’s happening in your arteries.

Angioplasty is a treatment. It opens blocked arteries. It often includes stent coronary placement.

You might have an angiogram and learn that you don’t need angioplasty. Or you might have an angiogram and immediately proceed to angioplasty during the same procedure.

Recovery and Aftercare coronary angioplasty

Here’s what’s wonderful about angioplasty: recovery is relatively quick.

After the procedure:

  • You’ll stay in the hospital overnight or possibly go home the same day
  • You’ll have a bandage over the catheter insertion site
  • You can resume light activities within a few days
  • You return to normal activities within 1-2 weeks
  • You’ll take medications to prevent clotting and manage your condition

Compared to open-heart surgery, this is minimal disruption to your life.

Types of Angioplasty

Standard Angioplasty (PTCA): Percutaneous Transluminal Coronary Angioplasty is the traditional form, often with stent placement (PTCA Stent). It works well for most blockages.

Specialized Procedures: For particularly challenging blockages, chip angioplasty (rotational atherectomy) might be used. This technique actually rotates a burr that smooths hardened plaque. It’s more specialized and requires experienced operators.

For chronic total occlusions arteries completely blocked specialized techniques might be employed.

Finding Your Specialist in Hyderabad

You need an experienced coronary artery disease doctor who performs angioplasty regularly. You need someone who has handled complications and knows how to navigate the most challenging cases.

The best angioplasty expert in India will have extensive training, excellent outcomes, and a compassionate approach to patient care. They’ll explain everything clearly, answer your questions, and work with you to determine whether angioplasty is truly the right choice for your situation.

In Hyderabad, you have access to heart specialists in Hyderabad who bring world-class expertise to this procedure.

Life After Angioplasty

You need to understand: angioplasty treats the blockage, but it doesn’t cure the underlying coronary artery disease. You’ll still need to:

  • Take medications as prescribed (usually including blood thinners, blood pressure medications, cholesterol medications)
  • Make lifestyle changes—diet, exercise, stress management
  • Stop smoking, if applicable
  • Control diabetes and blood pressure
  • Attend regular follow-ups

The good news? Most people do extremely well after angioplasty. Blood flow is restored. Symptoms improve dramatically. Quality of life increases significantly.

Possible Complications (Rare, But Real)

While generally safe, angioplasty does carry small risks:

  • Bleeding at the catheter site
  • Artery perforation
  • Allergic reaction to dye
  • Stent restenosis (renarrowing)
  • Blood clots

This is why you need an experienced operator and proper aftercare.

Also read: CHIP Angioplasty: Advanced Coronary Artery Disease Treatment Explained  

Prevention is still best.

Remember: the best treatment is prevention. If you don’t have coronary artery disease yet but are at risk, focus on:

  • Not smoking
  • Managing stress
  • Exercising regularly
  • Eating healthy
  • Maintaining healthy weight
  • Controlling blood pressure and cholesterol
  • Managing diabetes

Moving Forward coronary angioplasty Doctor

If you’re dealing with coronary artery disease, you’re not facing a death sentence. Modern interventions like angioplasty have revolutionized how we treat this condition. Many people go on to live full, active lives after successful angioplasty.

The key is working with experienced specialists who understand both the procedure and your individual circumstances.

Take the first step toward better heart health. Consult with Dr. C. Raghu, an experienced interventional cardiologist in Hyderabad specializing in coronary interventions. Schedule your appointment.
Call Us +91 95424 75650 


Dr raghu logo


Dr raghu logo


Call us now if you are in a medical emergency need, we will reply swiftly and provide you with a medical aid.


For Appointment with Dr Raghu: +91 80085 36699
Dr Raghu’s Patient Coordinator: +91 72860 10203
Dr Raghu’s Office Experience: +91 90001 65962
Dr Raghu’s Social Media Communication Channel: +91 97046 51708

Dr. Raghu | Heart Specialist in Hyderabad
Yashoda Hospitals, Raj Bhavan Road, Somajiguda, 1st floor, Room No. 115, Hyderabad -500082, Telangana

Best Cardiologists in Hyderabad


© 2024, Dr. Raghu. All rights reserved. Design & Developed by AMSDigital.in

[gtranslate]
+91-9542475650