Angioplasty-in-heart.jpg

October 26, 2026 AbhijitHearty Life

The days after angioplasty can feel unfamiliar

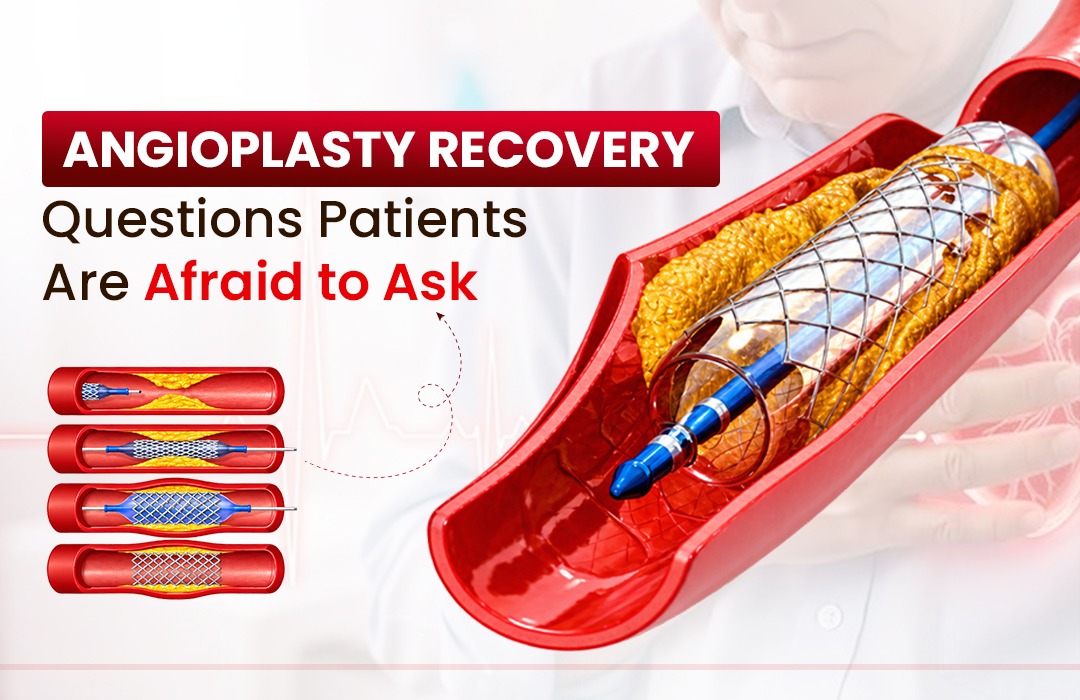
After angioplasty in heart arteries, people often feel relieved that a blocked or narrowed artery has been treated. Yet going home can bring a new set of worries. Is this soreness normal? Can I climb stairs? Which tablets are essential? Coronary angioplasty uses a catheter, commonly with a stent, to improve blood flow through a narrowed artery. It can be performed in different circumstances, including during treatment of a heart attack. Recovery instructions therefore vary. Your discharge plan, not somebody else’s experience, should guide what you do next.

For service information, see angioplasty in heart.

Which symptoms need urgent help?

Some bruising or tenderness where the catheter entered the body can occur, but increasing swelling or persistent bleeding requires prompt medical advice. If bleeding from the access site is heavy or does not stop after following the discharge team’s immediate first-aid instructions, seek emergency care. New severe chest pain, fainting, marked breathlessness or symptoms suggesting a stroke also require emergency assessment. Do not assume that every symptom is a normal part of healing. Know the emergency contact pathway before you leave hospital, and keep your discharge papers within easy reach.

For further reading, see coronary angioplasty.

What about walking, work and driving?

Many patients want a fixed number of days until life returns to normal. There is no single timeline. Recovery depends on why the procedure was done, whether there was a heart attack, where the catheter was inserted, other illnesses and any complications. Ask when you can walk outside, climb stairs, drive, resume sexual activity or lift heavy objects. Follow the access-site care instructions you received. Gradually increasing activity may be appropriate, and cardiac rehabilitation can help eligible patients rebuild confidence and adopt heart-healthy habits under supervision.

If you need a planned consultation, you can book an appointment with a cardiologist in Hyderabad to discuss the next step with a qualified clinician. This is not an emergency service.

The medicine question you should never skip

If a stent was placed, antiplatelet medicines are commonly prescribed to lower the risk of a clot forming inside it. The medicines and duration depend on your clinical situation. Never stop or change them without advice from the treating clinician, even if you feel well. Tell your care team about bleeding, bruising, stomach symptoms, other prescribed medicines, and any dental or surgical procedure being planned. Ask for a written medicine list with timing and purpose. This often reduces confusion when several family members help manage tablets.

Also read: Recovery After Angioplasty: Essential Heart Care Tips 

Small routines that make follow-up easier

Set up one place for the discharge sheet, medicine list, and follow-up date. If different family members help at home, agree on who checks prescriptions and who arranges visits. Keep an eye on the catheter access area according to your discharge instructions, and ask what level of bruising or discomfort is expected. If tiredness lasts longer than anticipated or you feel anxious about exertion, describe those concerns during follow-up instead of simply stopping activity. You should also ask whether cardiac rehabilitation is available and appropriate. A rehabilitation program may include supervised exercise, education, and support with risk factors. It is normal to need an explanation more than once: ask the care team to write down the plan in language you can follow. Recovery is safer when the information is clear and consistent.

Follow-up is part of treatment

Angioplasty treats a particular narrowing, but it does not remove every factor that can cause coronary artery disease. Follow-up commonly covers blood pressure, cholesterol, diabetes, smoking, movement, food choices, and ongoing symptoms. If you are deciding where to receive ongoing advice, look for a team that explains discharge instructions and whom to call when a problem arises. Dr. C. Raghu provides information about coronary procedures and consultation options on his website. For new or worsening symptoms, do not wait for a routine visit. A good recovery plan leaves you knowing both what to do each day and when to ask for help.

You can also check :-  Chip Cto angioplasty | Deep vein thrombosis | Heart Valve Screening
Angioplasty expert in India | Atrial Fibrillation treatment in Hyderabad | Cardiologist in india

Arrange a planned cardiology consultation

For non-emergency advice, request an appointment with Dr. C. Raghu, the best heart specialist in Hyderabad. 


Occlusion-Myocardial-Infarction-Symptoms-Treatment-1-1200x778.jpeg

August 3, 2026 AbhijitHearty Life

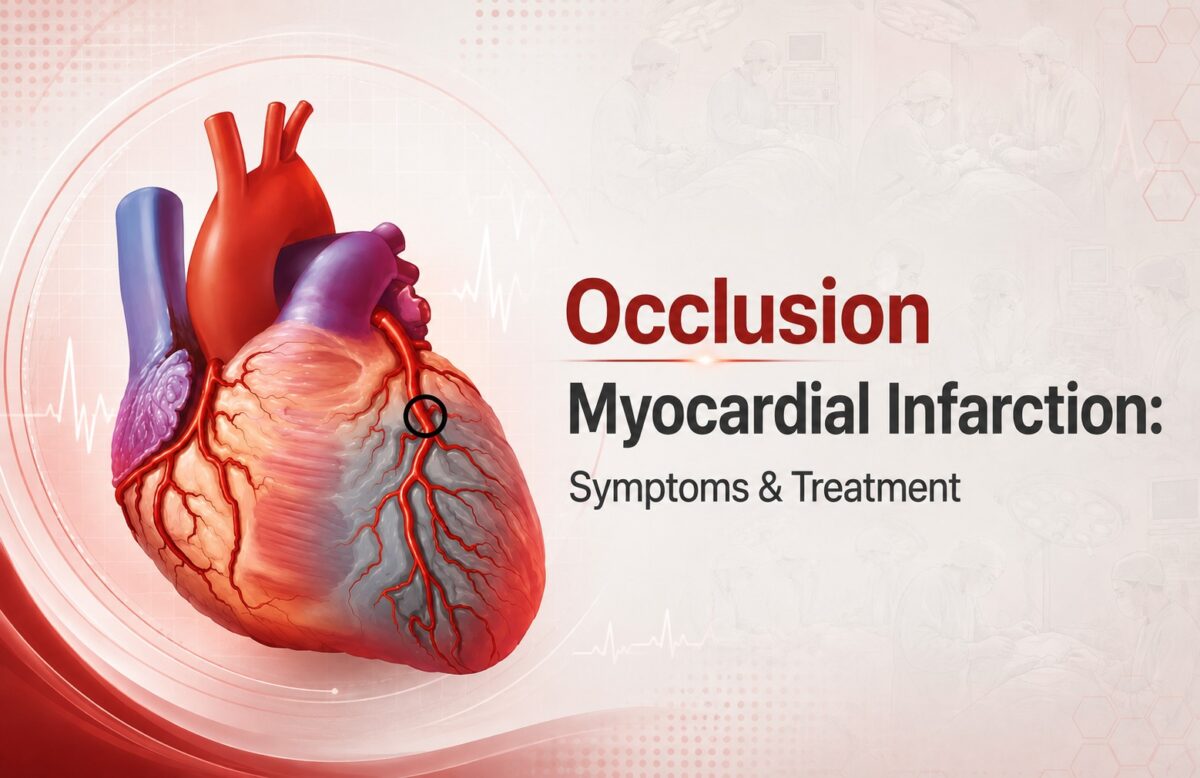
Occlusion myocardial infarction is a serious heart condition that occurs when a coronary artery becomes completely or significantly blocked, reducing or stopping blood flow to part of the heart muscle. Because prolonged loss of blood supply can cause permanent heart muscle damage, recognizing warning signs and getting emergency medical care quickly is extremely important.

For patients in Hyderabad, understanding the symptoms and treatment options can help them respond appropriately when a heart attack is suspected.

What Is Occlusion Myocardial Infarction?

A myocardial infarction, commonly called a heart attack, occurs when blood flow to the heart muscle is interrupted. In an occlusion myocardial infarction, a coronary artery may become completely blocked, often because a blood clot forms over a ruptured or damaged cholesterol plaque.

When oxygen-rich blood cannot reach the heart muscle, the affected tissue begins to become injured. The longer the artery remains blocked, the greater the potential for permanent heart damage.

This is why suspected heart attack symptoms should never be ignored or treated as simple indigestion, acidity, fatigue, or anxiety.

Common Symptoms of Occlusion Myocardial Infarction

Symptoms can vary between individuals, but common warning signs include:

  • Pressure, tightness, heaviness, or pain in the chest
  • Pain spreading to the arm, shoulder, back, neck, or jaw
  • Shortness of breath
  • Cold sweating
  • Nausea or vomiting
  • Unusual weakness or extreme tiredness
  • Dizziness or light-headedness
  • Rapid or irregular heartbeat
  • A feeling of anxiety or impending danger

Some people, particularly older adults and those with diabetes, may experience less typical symptoms. Chest discomfort may also be mild rather than severe.

If symptoms suggest a heart attack, seeking emergency medical attention immediately is more important than trying to identify the exact cause at home.

What Causes a Coronary Artery Occlusion?

Several factors can contribute to coronary artery blockage. One of the most common causes is coronary artery disease, where fatty deposits gradually accumulate inside the arteries.

Risk factors include:

  • High cholesterol
  • High blood pressure
  • Diabetes
  • Smoking or tobacco use
  • Obesity
  • Physical inactivity
  • Unhealthy diet
  • Family history of heart disease
  • Increasing age
  • Chronic stress
  • Previous cardiovascular disease

A plaque inside a coronary artery can sometimes rupture suddenly. The body may respond by forming a blood clot, which can rapidly restrict or completely stop blood flow.

How Is Occlusion Myocardial Infarction Diagnosed?

Doctors use several tests to determine whether a patient is experiencing a heart attack and to understand the severity of the blockage.

Electrocardiogram (ECG)

An ECG records the heart’s electrical activity and can identify patterns associated with acute coronary artery blockage.

Blood Tests

Cardiac biomarkers, particularly troponin, can help determine whether heart muscle injury has occurred.

Echocardiogram

An echocardiogram uses ultrasound to evaluate heart structure and function. It can help doctors identify areas of the heart that are not contracting normally.

Coronary Angiography

Coronary angiography allows doctors to examine the coronary arteries and identify significant narrowing or blockage. It can also help guide treatment decisions.

Treatment for Occlusion Myocardial Infarction

Treatment depends on the patient’s condition, the location and severity of the blockage, and how quickly medical care is provided.

Emergency Medical Treatment

Doctors may use medications to reduce clot formation, improve blood flow, control pain, and stabilize the patient’s condition.

Coronary Angioplasty and Stenting

For an acutely blocked coronary artery, percutaneous coronary intervention (PCI) may be performed. During the procedure, a catheter is guided into the affected artery. A balloon can be used to open the narrowed area, and a stent may be placed to help maintain blood flow.

Rapid restoration of blood flow is an important goal in appropriate patients with an acute coronary artery occlusion.

Additional Treatment

Depending on the patient’s cardiovascular risk and overall health, treatment may also include medicines for cholesterol, blood pressure, blood clot prevention, and other underlying conditions.

After the acute event, lifestyle changes and cardiac rehabilitation may play an important role in reducing future cardiovascular risk.

Also read:  What is chronic total occlusion? Under Chip CTO angioplasty  

Why Time Matters During a Heart Attack

Heart muscle requires a continuous supply of oxygen-rich blood. When a coronary artery becomes blocked, the affected muscle can progressively become damaged.

For this reason, people experiencing possible heart attack symptoms should not wait for symptoms to disappear on their own. Delaying medical evaluation can reduce the opportunity for timely treatment.

If someone develops severe or persistent chest discomfort, breathlessness, sweating, fainting, or pain spreading to the arm, jaw, back, or shoulder, emergency medical care should be sought immediately.

Choosing a Heart Specialist in Hyderabad

Patients dealing with suspected or diagnosed coronary artery disease may need evaluation by an experienced cardiologist in Hyderabad. A heart specialist in Hyderabad can assess cardiovascular risk factors, interpret diagnostic tests, and recommend an appropriate treatment strategy.

For patients with complex coronary conditions, specialist evaluation can help determine whether medication, coronary angioplasty, stenting, or another intervention is appropriate.

Searching for a myocardial cardiologist in Hyderabad may also lead patients to specialists who manage heart attacks and other coronary artery conditions.

Can Occlusion Myocardial Infarction Be Prevented?

Not every heart attack can be prevented, but many cardiovascular risk factors can be managed.

Helpful measures include:

  • Controlling blood pressure and cholesterol
  • Managing diabetes effectively
  • Avoiding smoking and tobacco
  • Maintaining a healthy body weight
  • Following a heart-healthy diet
  • Exercising according to medical advice
  • Taking prescribed medicines regularly
  • Attending recommended cardiovascular check-ups
  • Recognizing and acting on warning symptoms promptly

People with known heart disease or multiple cardiovascular risk factors should discuss an appropriate prevention plan with their doctor.

Read more: What Is Atrial Fibrillation? Understanding AFib Simply 

When Should You Seek Emergency Care?

Chest pain or discomfort should never be ignored when it is sudden, severe, persistent, or accompanied by symptoms such as breathlessness, sweating, nausea, dizziness, or pain radiating to the arm or jaw.

Do not wait for symptoms to become severe before seeking emergency medical attention.

Occlusion myocardial infarction can become life-threatening when blood flow to the heart is significantly interrupted. Early recognition, rapid diagnosis, and timely treatment can make a critical difference.

Consult Dr. C. Raghu

If you are concerned about coronary artery disease, heart attack symptoms, or other cardiovascular problems, consultation with an experienced cardiology specialist can help with appropriate evaluation and treatment planning.

Dr. C. Raghu is a senior interventional cardiologist associated with advanced cardiac care in Hyderabad and Secunderabad.

Watch the video to review the discussion on occlusive myocardial infarction and acute coronary syndrome: https://youtu.be/jWvP0BG2bsY

For more information about cardiac care and interventional cardiology services,

Important: This article is intended for general educational purposes and does not replace professional medical advice. If you or someone around you has symptoms suggestive of a heart attack, seek emergency medical care immediately.


chronic-total-occlusion.webp

July 23, 2026 AbhijitHearty Life

Chip cto angioplasty You’ve had blockages in your arteries for a while. You’ve had procedures. You’ve taken medications. And yet your doctor just told you that you have a completely blocked artery—what’s called a chronic total occlusion. The artery isn’t just narrowed. It’s not just severely blocked. It’s completely shut off.

Your first thought is panic. But before you despair, understand this: CTO doesn’t mean you’re out of options. It doesn’t mean your case is hopeless. Modern medicine has developed specialized techniques to open even completely blocked coronaries. But you need to understand what CTO is and how it’s treated.

Understanding Coronary Artery Disease Progression

Remember how coronary artery disease develops? Plaque builds up in your arteries over time. This usually happens over years or decades.

In some people, this process is gradual. The blockage slowly increases from 50% to 75% to 90%. At each stage, blood can still squeeze through, though less efficiently.

But sometimes, the blockage continues increasing until the artery is completely sealed. No blood flows through at all. This is a chronic total occlusion—or CTO.

The word “chronic” is important. It means this blockage didn’t just happen. It’s been there for a while—usually at least three months. Your body has actually adapted somewhat, sometimes developing other small blood vessels that partially compensate for the blocked artery.

Why CTO Causes Problems

Chronic Total Occlusion Treatment

You might think, “If blood develops alternative routes, why is CTO a problem?”

Here’s why it matters:

The alternative blood vessels are limited. They don’t fully replace the original artery’s function.

Your heart remains oxygen-starved. You still experience angina (chest pain) during exertion. You still feel fatigued.

Your heart remains vulnerable. If another artery narrows, your heart has fewer reserves.

It contributes to heart failure. Prolonged oxygen deprivation weakens your heart muscle.

It increases heart attack risk. The blocked artery region is particularly vulnerable to sudden deterioration.

Also read:  Blood Clots in AFib: How They Form and Prevention 

The Challenge of Chip CTO Angioplasty Treatment

Why don’t doctors simply reopen CTOs in everyone? Because it’s technically difficult.

When an artery is completely blocked, your doctor can’t thread a wire through the blockage the way they do with partially blocked arteries. The wire hits a dead end and can’t advance.

Recanalization—opening a completely blocked artery—requires specialized expertise, specialized equipment, and particular skill. Not all interventional cardiologists perform CTO procedures. It’s a specialized subset within the specialty.

CTO Angioplasty: How It Works

If you’re a good candidate for CTO angioplasty, here’s what happens:

Step One: Imaging Your doctor performs coronary angiography to visualize the completely blocked artery. They determine the length of the blockage, its characteristics, and whether it’s a suitable target for recanalization.

Step Two: Wire Navigation This is where it gets technical. The doctor advances a guidewire toward the blockage. When the wire hits resistance, specialized techniques are used:

  • Antegrade approach: threading through from the proximal end
  • Retrograde approach: threading backwards from a collateral (alternative) vessel
  • Combination approaches: sometimes both directions are attempted

Step Three: Channel Creation Using controlled force and specialized tools, a pathway is created through the blockage. Various devices might be used—rotating burrs (chip CTO angioplasty), laser devices, or mechanical tools.

Step Four: Balloon Dilation Once a pathway is established, balloons are advanced and inflated to widen the channel.

Step Five: Stent Placement A stent—usually a coronary stent with drug-eluting properties—is placed to maintain the opening and prevent restenosis.

The Technical Complexity

CTO recanalization requires:

  • Specialized training (often fellowship training beyond standard cardiology)
  • Specialized equipment (multiple types of wires, catheters, and devices)
  • Extended procedure time (CTOs often take 2-4 hours)
  • Patience and problem-solving skills
  • Access to backup surgical support if something goes wrong

This is why CTO angioplasty is performed by a limited number of specialists, often at major cardiac centers.

When CTO Treatment is Recommended

Your coronary artery disease doctor might recommend recanalization if:

  • You have symptoms—angina, shortness of breath, exercise limitation
  • The blocked artery supplies significant heart muscle
  • You’re otherwise a good candidate
  • You’re willing to undergo the specialized procedure

Some CTOs are left alone. If you have good alternative blood supply and minimal symptoms, your doctor might say observation is appropriate. But if you’re symptomatic or at high risk, recanalization should be discussed.

Success Rates and Outcomes

Modern CTO recanalization is quite successful. Success rates typically range from 70-90% at experienced centers, depending on the complexity of the blockage.

When successful:

  • Symptoms improve dramatically
  • Exercise tolerance increases
  • Quality of life improves significantly
  • Your heart’s function often improves
  • Your long-term prognosis improves

The Different CTO Techniques

Antegrade Approach Your doctor works from the proximal (near your heart) end of the blockage, advancing a wire and devices distally (away from your heart).

Retrograde Approach Your doctor uses collateral vessels—alternative blood vessels—to approach the blockage from the distal end, working backwards toward your heart.

Hybrid Approach Your doctor switches between antegrade and retrograde techniques, using whichever works best as the procedure progresses.

Specialized Procedures For particularly challenging blockages, specialized techniques like chip angioplasty (rotational atherectomy) might be employed. These techniques use rotating burrs or lasers to grind away hardened plaque.

Finding a CTO Specialist

Not every coronary artery disease specialist performs CTO recanalization. You need someone with specific expertise.

The best angioplasty expert in India who handles CTOs will have:

  • Dedicated CTO training
  • High success rates (preferably >80%)
  • Low complication rates
  • Extensive experience (hundreds of CTO procedures)
  • Access to all necessary equipment
  • Support from surgical backup
  • Genuine expertise and not just willingness to try

In Hyderabad, a few centers have true CTO expertise. Ensure your angioplasty expert in Hyderabad has specific CTO experience.

Risks and Complications

CTO procedures do carry risks:

  • Perforation of the artery (usually manageable)
  • Contrast-induced kidney injury
  • Stroke (rare)
  • Heart attack during procedure
  • Access site bleeding
  • Unsuccessful recanalization (wire can’t get through despite attempts)

At specialized centers with experienced operators, major complications are rare (2-5%).

Life After CTO Recanalization

If your CTO is successfully recanalized:

  • You’ll feel better relatively quickly
  • Medications will be adjusted
  • A stent is now in place, requiring antiplatelet therapy
  • Regular follow-ups ensure your stent is functioning well
  • Your heart function may improve over weeks to months

Most people experience significant quality of life improvement.

If Recanalization Isn’t Possible

Sometimes, despite best efforts, the wire can’t traverse a CTO. In this case:

  • Your doctor will stop and not force the issue
  • You’ll continue medical management
  • Other treatments might be considered—medication optimization, other interventions if different arteries are treatable
  • You’ll need close follow-up

This isn’t failure. CTO anatomy varies, and some blockages are simply too difficult. Your doctor’s decision to stop is actually protecting you.

Prevention and Management

Going forward, focus on:

  • Medications—take them exactly as prescribed
  • Lifestyle changes—diet, exercise, stress management
  • Smoking cessation if applicable
  • Managing diabetes and hypertension
  • Regular follow-ups and testing
  • Addressing other coronary blockages

Your Path Forward

Chronic total occlusion sounds intimidating. But with modern techniques and experienced specialists, CTOs are increasingly manageable. Many people who thought their blockage couldn’t be opened are now living symptom-free lives after successful CTO recanalization.

The key is finding a coronary artery disease doctor with genuine CTO expertise and being realistic about what’s possible.

Also read: What is coronary angioplasty? Everything you need to know
Also read: CHIP Angioplasty: Advanced Coronary Artery Disease Treatment Explained 


If you have a chronic total occlusion or complex coronary disease, expert care makes a difference. Consult with Dr. C. Raghu, an interventional cardiologist with expertise in complex coronary interventions.


Coronary-angioplasty-2.webp

Coronary angioplasty: Your chest feels tight. You’ve been getting shortness of breath lately, especially when you climb stairs or walk briskly. You’re worried. Your doctor has mentioned something called coronary angioplasty, but you don’t understand what it is or whether you really need it.

You’re not alone. Many middle-aged people are facing coronary artery disease without fully understanding their treatment options. The term “angioplasty” sounds intimidating. The word “stent” makes you nervous. But here’s the truth: understanding what these procedures are and how they can help you is empowering. It gives you control over your health decisions.

Understanding Coronary angioplasty Artery Disease
Coronary angioplasty

Before we discuss angioplasty, you need to understand the problem it solves.

Your heart is a muscle that needs oxygen to work. Coronary arteries deliver oxygen-rich blood to your heart. These are the highways of your cardiovascular system. Over time, for various reasons—high cholesterol, high blood pressure, smoking, diabetes, and stress—fatty deposits build up inside these arteries. This buildup is called plaque.

Coronary artery disease happens when these arteries narrow. Blood flow decreases. Your heart struggles to get enough oxygen, especially during activity or stress. You feel chest pain. You feel exhausted. You feel vulnerable.

This is serious. Completely blocked arteries lead to heart attacks.

What Exactly is Coronary Angioplasty?

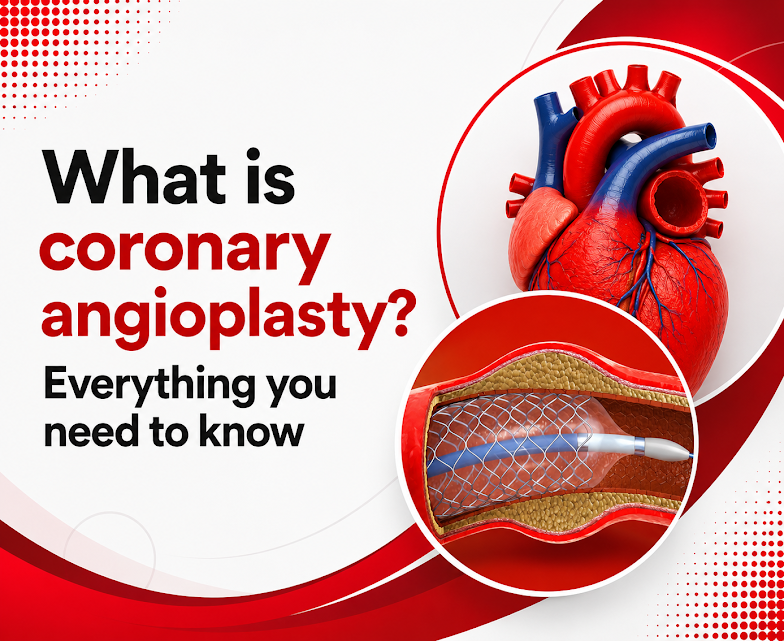
Let’s demystify this. Coronary angioplasty is a minimally invasive procedure that opens blocked or narrowed coronary arteries. It’s not surgery in the traditional sense—no large incisions, no general anesthesia, no weeks of recovery.

Here’s how it works:

Step One: Angiogram Your coronary artery disease doctor first performs an angiogram. A thin catheter (tube) is inserted through an artery in your groin or arm. This catheter is guided to your heart. A special dye is injected through the catheter, and X-rays are taken. These images show exactly where your arteries are blocked or narrowed. You’re awake during this procedure, though mildly sedated.

Step Two: Balloon Inflation Once the blocked area is identified, a balloon catheter is advanced to that location. When the catheter is in position, the balloon is inflated. This balloon pushes the plaque against the artery wall, widening the artery and restoring blood flow. You might feel slight chest discomfort—this is normal and temporary.

Step Three: Stent Placement In most modern angioplasty procedures, a stent is placed. Think of a stent as a tiny mesh tube. It keeps the artery open after the balloon is removed, preventing the artery from narrowing again. Most stents today are drug-eluting, meaning they release medication that prevents scar tissue buildup.

The entire procedure typically takes 30 minutes to an hour.

Why Your Doctor Recommends Angioplasty

Your coronary artery disease specialist recommends angioplasty for specific reasons:

  • You have significant blockages causing symptoms
  • You have blockages that could cause a heart attack
  • Medical management (medications) isn’t sufficient
  • You’ve had a recent heart attack
  • You’re having a heart attack right now

Not all coronary artery disease requires angioplasty. Some people do well with medications. But when angioplasty is appropriate, it can be life-changing.

Also read: Pulmonary Embolism in India: Emergency & Finding Specialist  

The Difference Between Angioplasty and Angiogram

Many people confuse these terms. Let me clarify:

An angiogram is a diagnostic test. It shows what’s happening in your arteries.

Angioplasty is a treatment. It opens blocked arteries. It often includes stent coronary placement.

You might have an angiogram and learn that you don’t need angioplasty. Or you might have an angiogram and immediately proceed to angioplasty during the same procedure.

Recovery and Aftercare coronary angioplasty

Here’s what’s wonderful about angioplasty: recovery is relatively quick.

After the procedure:

  • You’ll stay in the hospital overnight or possibly go home the same day
  • You’ll have a bandage over the catheter insertion site
  • You can resume light activities within a few days
  • You return to normal activities within 1-2 weeks
  • You’ll take medications to prevent clotting and manage your condition

Compared to open-heart surgery, this is minimal disruption to your life.

Types of Angioplasty

Standard Angioplasty (PTCA): Percutaneous Transluminal Coronary Angioplasty is the traditional form, often with stent placement (PTCA Stent). It works well for most blockages.

Specialized Procedures: For particularly challenging blockages, chip angioplasty (rotational atherectomy) might be used. This technique actually rotates a burr that smooths hardened plaque. It’s more specialized and requires experienced operators.

For chronic total occlusions arteries completely blocked specialized techniques might be employed.

Finding Your Specialist in Hyderabad

You need an experienced coronary artery disease doctor who performs angioplasty regularly. You need someone who has handled complications and knows how to navigate the most challenging cases.

The best angioplasty expert in India will have extensive training, excellent outcomes, and a compassionate approach to patient care. They’ll explain everything clearly, answer your questions, and work with you to determine whether angioplasty is truly the right choice for your situation.

In Hyderabad, you have access to heart specialists in Hyderabad who bring world-class expertise to this procedure.

Life After Angioplasty

You need to understand: angioplasty treats the blockage, but it doesn’t cure the underlying coronary artery disease. You’ll still need to:

  • Take medications as prescribed (usually including blood thinners, blood pressure medications, cholesterol medications)
  • Make lifestyle changes—diet, exercise, stress management
  • Stop smoking, if applicable
  • Control diabetes and blood pressure
  • Attend regular follow-ups

The good news? Most people do extremely well after angioplasty. Blood flow is restored. Symptoms improve dramatically. Quality of life increases significantly.

Possible Complications (Rare, But Real)

While generally safe, angioplasty does carry small risks:

  • Bleeding at the catheter site
  • Artery perforation
  • Allergic reaction to dye
  • Stent restenosis (renarrowing)
  • Blood clots

This is why you need an experienced operator and proper aftercare.

Also read: CHIP Angioplasty: Advanced Coronary Artery Disease Treatment Explained  

Prevention is still best.

Remember: the best treatment is prevention. If you don’t have coronary artery disease yet but are at risk, focus on:

  • Not smoking
  • Managing stress
  • Exercising regularly
  • Eating healthy
  • Maintaining healthy weight
  • Controlling blood pressure and cholesterol
  • Managing diabetes

Moving Forward coronary angioplasty Doctor

If you’re dealing with coronary artery disease, you’re not facing a death sentence. Modern interventions like angioplasty have revolutionized how we treat this condition. Many people go on to live full, active lives after successful angioplasty.

The key is working with experienced specialists who understand both the procedure and your individual circumstances.

Take the first step toward better heart health. Consult with Dr. C. Raghu, an experienced interventional cardiologist in Hyderabad specializing in coronary interventions. Schedule your appointment.
Call Us +91 95424 75650 


Coronary-Artery-Disease-in-India.jpg

May 15, 2026 AbhijitHearty Life

Coronary artery disease (CAD) kills more Indians than any other single condition. It strikes earlier in the Indian population than in Western countries, often a decade sooner,  driven by a combination of genetic susceptibility to dyslipidemia and insulin resistance, high rates of diabetes, rising rates of obesity and physical inactivity, tobacco use, and a diet increasingly influenced by processed food.

Yet the treatment available today — when coronary artery disease is detected early enough and managed by a skilled coronary artery disease specialist — is remarkably effective. Coronary angioplasty in heart arteries, supported by modern drug-eluting stents and evidence-based medication, gives patients with even severe coronary disease a very real path back to normal life.

The barrier is not treatment availability. It is awareness: patients who do not know the symptoms, who dismiss warning signs, or who do not understand what a coronary angioplasty and angiogram involve delay seeking help in ways that cost them heart muscle, cardiac function, and, sometimes, their lives.

This guide walks every reader through the complete pathway from recognizing symptoms through the diagnostic angiogram to PTCA stent placement and recovery—because understanding this pathway is genuinely life-saving.

Also read: Understanding PTCA Stent & Coronary Angioplasty expert

What Happens in Coronary Artery Disease

coronary artery disease

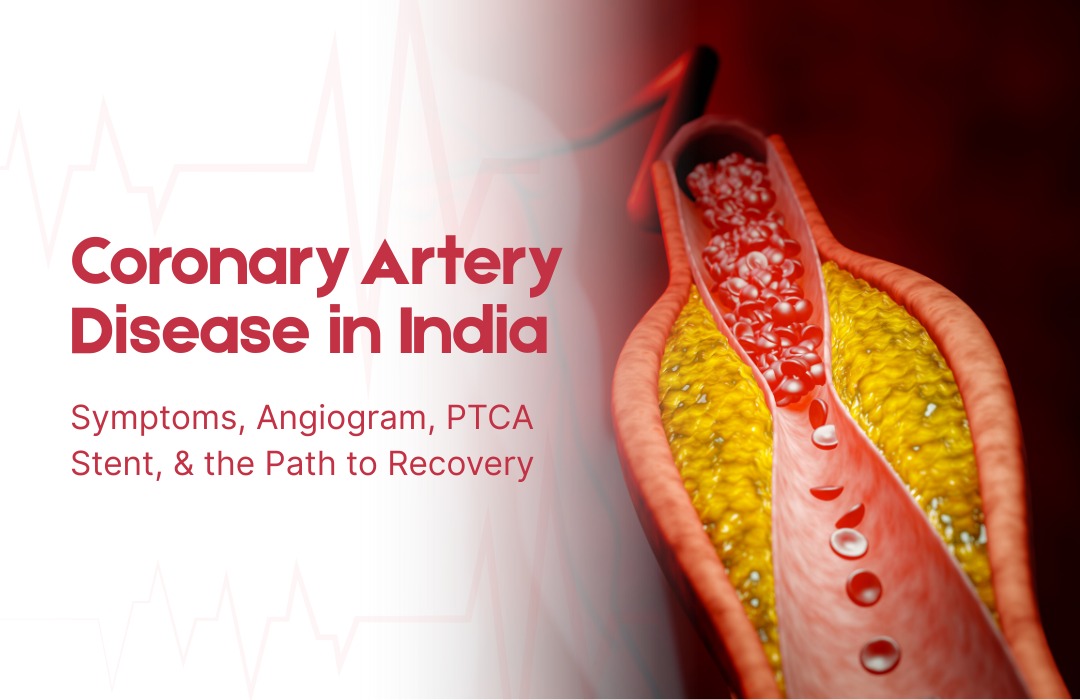
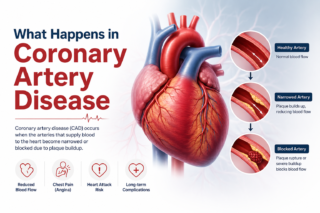
Coronary arteries are the three main blood vessels that supply oxygenated blood to the heart muscle itself. Coronary artery disease is the progressive accumulation of atherosclerotic plaque deposits of cholesterol, inflammatory cells, calcium, and connective tissue within the walls of these arteries. As plaques grow, they narrow the artery’s lumen, reducing the volume of blood the heart muscle receives.

In early disease, there are no symptoms. As narrowings become significant, the heart muscle receives adequate blood at rest but insufficient blood during exertion, producing the symptom of stable angina. When a plaque ruptures suddenly, as can happen without warning at any level of physical exertion, it triggers the formation of an acute blood clot that can completely block the artery, causing a heart attack 

Heart attacks cause permanent heart muscle damage in proportion to the time the artery remains blocked. Opening the blocked artery within 90 minutes of symptom onset with emergency coronary angioplasty (primary PCI) salvages the most muscle and produces the best survival outcomes. Every minute matters.

Recognising the Symptoms: What to Know, and What to Take Seriously

Stable angina is exertional chest discomfort—a tightness, pressure, heaviness, or aching in the center of the chest that appears predictably during physical activity (walking uphill, climbing stairs, carrying loads) and relieves with rest within a few minutes. It may radiate to the left arm, jaw, or back.

In the Indian population, and particularly in patients with diabetes, coronary artery disease sometimes presents atypically without classic chest pain,but with unexplained breathlessness on exertion, unusual fatigue, or a feeling of heaviness or indigestion. These symptoms in any patient with cardiovascular risk factors deserve a prompt cardiac evaluation, not reassurance.

Acute coronary syndromes,  unstable angina and heart attack, present with chest discomfort that is more severe and longer-lasting (more than 20 minutes) and may occur at rest. Associated symptoms, including sweating, nausea, breathlessness, or syncope, increase the likelihood of an acute event. These symptoms require immediate emergency care calling an ambulance and going directly to the nearest hospital capable of emergency coronary angioplasty in heart arteries.

The Diagnostic Pathway: From Symptom to Angiogram

The investigation of stable chest pain begins with clinical history, examination, a resting ECG, and blood tests. An echocardiogram assesses left ventricular function and wall motion. Stress testing exercises, ECG, stress echocardiogram, or nuclear perfusion imaging demonstrates whether coronary disease is causing ischemia during physical stress.

When an investigation suggests significant coronary artery disease, or when a patient presents with an acute coronary syndrome, coronary angiography is performed. This angioplasty and angiogram procedure takes 20 to 40 minutes under local anesthesia and sedation, with a catheter inserted through the radial artery in the wrist to deliver contrast dye into the coronary arteries while X-ray images map the distribution and severity of narrowings.

CT coronary angiography, a noninvasive alternative using CT scanning, is increasingly used as an initial anatomical investigation in stable patients with intermediate pretest probability of significant coronary disease, providing detailed arterial mapping without catheter insertion.

Also read: 5 Signs You or Your Elderly Parent May Need a Heart Valve Replacement  

PTCA Stent: What the Procedure Involves Step by Step

When the angiogram reveals a narrowing that warrants treatment, angioplasty with PTCA stent deployment proceeds as follows:

A guidewire, a very thin, flexible wire, is advanced through the catheter and across the coronary narrowing. The wire serves as a rail for all subsequent equipment. A balloon catheter is advanced over the wire to the lesion site and inflated to compress the plaque, widening the arterial lumen. A drug-eluting stent coronary device, a metal mesh cylinder mounted on a second balloon, is then advanced to the same position and expanded, embedding itself in the artery wall and remaining in place permanently as a scaffold.

After stent deployment, the operator assesses the result using post-deployment balloon inflation to optimize expansion and intravascular imaging (IVUS or OCT) in many cases to confirm optimal stent apposition. Haemodynamic measurements confirm normal blood flow before all equipment is removed.

For heavily calcified lesions that require special preparation before stenting, chip angioplasty techniques, including intravascular lithotripsy or rotational atherectomy, are deployed to modify the calcium and allow adequate stent expansion.
The entire procedure for a straightforward single-vessel case typically takes 45 to 90 minutes.

Recovery: Life After a Coronary Stent

Recovery from coronary angioplasty is rapid compared to surgical alternatives. Most patients return to light daily activities within one to two weeks and to full activity within two to four weeks.

The most critical post-stent requirement is medication adherence. Dual antiplatelet therapy, aspirin combined with a second agent (clopidogrel, prasugrel, or ticagrelor), is prescribed for a defined period to prevent stent thrombosis. The duration depends on stent type and clinical risk profile. Stopping this medication early without medical guidance carries a risk of acute stent occlusion and must be avoided.

Long-term coronary artery disease management, statins, blood pressure treatment, diabetes optimization, and lifestyle modification continue indefinitely regardless of whether a stent has been placed. A stent treats the obstruction; it does not cure the underlying disease. Regular follow-up with the treating coronary artery disease doctor is essential for monitoring disease progression and adjusting treatment as needed.

Dr. C Raghu: Comprehensive Coronary Artery Disease Care in Hyderabad

Dr. C. Raghu coronary artery disease program in Hyderabad encompasses the full clinical pathway from initial risk assessment and non-invasive investigation through coronary angiography and complex coronary angioplasty to long-term secondary prevention management. His practice uses intravascular imaging and physiological assessment tools routinely, reflects current evidence-based guidelines in every decision, and provides clear, patient-centered communication throughout every stage of the diagnostic and treatment process.

For advanced coronary artery disease treatment, coronary angioplasty, and PTCA stent care in Hyderabad, consult Dr. C. Raghu at Yashoda Hospitals, Secunderabad — Call +91 95424 75650 today for expert cardiac care.


Best-Angioplasty-Expert-in-India.webp

May 13, 2026 AbhijitHearty Life

India’s Coronary Disease Crisis — and Why the Quality of the Doctor Matters

Angioplasty expert in India Coronary artery disease is the leading cause of death in India. The country bears one of the world’s highest burdens of coronary disease, presenting at younger ages than Western populations and frequently at more advanced stages of disease. Every year, hundreds of thousands of Indians undergo coronary angioplasty, the catheter-based procedure to open blocked heart arteries, as a treatment for chest pain, heart attacks, and significant coronary disease discovered on investigation.

The outcome of that angioplasty, whether it relieves symptoms effectively, whether the stent lasts, whether the vessel stays open, or whether complications are managed safely, depends enormously on the quality of the operator. Not all interventional cardiologists are equal. The gap between the best angioplasty experts in India and average operators is meaningful, and that gap is most visible in exactly the cases where it matters most: complex lesions, challenging anatomy, and patients with multiple co-existing conditions.

This article explains what genuinely separates the best angioplasty experts in India from the rest — using plain language, grounded in evidence, because patients who understand these distinctions make better decisions about their own care.

What Coronary Angioplasty Actually Is

Coronary angioplasty, formally called Percutaneous Coronary Intervention (PCI) and historically known as PTCA (Percutaneous Transluminal Coronary Angioplasty), is a catheter-based procedure to open narrowed or blocked coronary arteries that supply blood to the heart muscle.

Under local anesthesia and light sedation, a catheter is inserted through the radial artery in the wrist (the modern preferred access route) or the femoral artery in the groin and navigated under X-ray guidance to the blocked coronary artery. A tiny balloon is inflated at the site of the blockage to compress the obstructing plaque and widen the artery. A PTCA stent  a small metal mesh cylinder  is then deployed at the same site to hold the artery open permanently.

Modern drug-eluting stents, which release medication over several months to prevent re-narrowing at the treated site, have dramatically improved the long-term success rates of coronary angioplasty. Complex cases involving heavily calcified plaques benefit from specialized techniques, including chip angioplasty using intravascular lithotripsy, cutting balloons, or rotational atherectomy, that the best angioplasty experts in Hyderabad are trained and equipped to deploy.

Also read : Meet Cardiologist in India, Dr C. Raghu Yashoda, Somajiguda 

Differentiator 1: Case Volume and Complexity Range

The relationship between operator volume and patient outcomes in interventional cardiology is one of the most extensively documented findings in all of medicine. Operators who perform a high annual volume of coronary angioplasty procedures make fewer technical errors, handle complications more adeptly, make better judgments about when to intervene and when not to, and produce measurably better outcomes across virtually every clinical metric.

This is particularly important in complex cases. Single-vessel, non-calcified, easily accessed coronary lesions in otherwise healthy patients are manageable for most trained interventionalists. Multivessel disease, chronic total occlusion recanalization, left main coronary stenting, severely calcified lesions requiring chip angioplasty techniques, and patients with prior coronary artery bypass surgery  these cases require accumulated experience that only comes with high-volume practice.

When a patient has complex coronary artery disease, the choice of a high-volume complex PCI operator is not a luxury. It is a clinical necessity that affects outcomes.

Differentiator 2: Intravascular Imaging Guidance

Coronary angiography — the standard X-ray imaging of coronary arteries using contrast dye — shows where narrowings are and how severe they appear. But it provides only a two-dimensional silhouette view of a three-dimensional structure. It cannot reliably assess plaque composition, calcium distribution, stent expansion, or stent apposition to the vessel wall.

Intravascular imaging — specifically intravascular ultrasound (IVUS) and optical coherence tomography (OCT) — provides cross-sectional views inside the artery in high resolution, allowing the angioplasty expert to see inside the vessel in three dimensions, choose the correct stent size, guide deployment, verify optimal expansion, and identify and correct problems before the patient leaves the catheterization laboratory.

Multiple large randomized trials and registry studies have confirmed that intravascular imaging-guided PCI is associated with lower rates of stent thrombosis, lower rates of target vessel failure, and better long-term clinical outcomes compared to angiography-guided PCI alone. An angioplasty expert in India who routinely uses intravascular imaging is practicing at a higher standard than one who relies on angiography alone.

Differentiator 3: Physiological Assessment of Lesion Severity

Not every coronary narrowing visible on an angioplasty and angiogram needs to be treated with a stent. Coronary angiography sometimes makes narrowings look more severe or less severe than they physiologically are. Treating a narrowing that does not cause ischemia (inadequate blood supply to heart muscle) with a stent exposes the patient to the risks of the procedure without providing clinical benefit.

Fractional Flow Reserve (FFR) and instantaneous Wave-Free Ratio (iFR) are wire-based physiological measurements that assess whether a coronary narrowing is causing clinically significant ischemia. Multiple trials — DEFER, FAME, FAME 2, and iFR-SWEDEHEART — have established that FFR- and iFR-guided PCI is superior to angiography-guided PCI in reducing unnecessary procedures while improving outcomes in lesions that truly require treatment.

A coronary heart disease doctor who uses physiological assessment to guide stent decisions is practicing evidence-based medicine at a higher standard than one who relies solely on the visual appearance of angiography.

Differentiator 4: Honest Decision-Making About When Not to Stent

Perhaps the most underappreciated quality of the best angioplasty experts in India is their willingness to recommend against angioplasty when the evidence does not support it. Major trials — ISCHEMIA, COURAGE, BARI 2D — have demonstrated that in patients with stable coronary artery disease and good left ventricular function, optimal medical therapy alone can produce outcomes equivalent to PCI for preventing heart attacks and death, while PCI reliably provides better symptom relief.

A coronary artery disease specialist who presents these findings honestly, explains that a stent will relieve angina but may not prolong life in stable disease, and supports the patient in making an informed choice rather than defaulting to the most immediately available intervention is providing genuinely excellent, patient-centered care.

This kind of honest decision-making is a marker of clinical confidence and integrity that patients should look for and value.

Also read: CHIP Angioplasty: Advanced Coronary Artery Disease Treatment Explained 

Emergency Angioplasty: The Time-Critical Dimension

The most time-sensitive application of coronary angioplasty is primary PCI the emergency procedure to open a blocked artery during an acute heart attack (STEMI ST-elevation myocardial infarction). Primary PCI must be performed within 90 minutes of hospital arrival to minimize heart muscle damage and improve survival. Every minute of delay costs irreplaceable cardiac muscle.

An angioplasty expert in Hyderabad who participates in a 24/7 primary PCI program on call around the clock, working in a center with rapid cath lab activation protocols, demonstrates the kind of commitment to acute cardiac care that defines a truly comprehensive coronary program. Dr. Raghu practice maintains this emergency PCI capability, ensuring that patients with acute coronary syndromes receive the most time-critical interventional care when it is needed most.

Dr. Raghu: The Standard of Excellence in Coronary Angioplasty in Hyderabad

Dr. C Raghu brings to his coronary angioplasty practice a combination of high case volume, routine intravascular imaging and physiological lesion assessment, mastery of complex PCI techniques, including chip angioplasty for calcified lesions, and an evidence-based communication approach that helps patients understand exactly when angioplasty adds value to their treatment and when other options deserve equal consideration.

His patients  from simple stable coronary disease to the most complex multivessel and chronic total occlusion cases — receive a consistently high standard of evaluation, procedural care, and long-term follow-up.

Contact Dr.C Raghu’s team cardiologist in Hyderabad through to schedule a coronary artery disease evaluation or angioplasty consultation.

About Dr. C. Raghu

Dr. C. Raghu — MD, DM, FESC, FACC, FSCAI
Interventional Cardiologist | Yashoda Hospital, Raj Bhavan Road, Somajiguda, 1st Floor, Room No. 115, Hyderabad – 500082, Telangana

Specialisation: Coronary, Vascular & Structural Interventions | TAVR | CHIP Angioplasty | Complex Coronary Procedures

OPD: Monday to Saturday, 8 AM – 8 PM  |  Emergency: 24/7  |  +91 95424 75650  |


Dr raghu logo


Dr raghu logo


Call us now if you are in a medical emergency need, we will reply swiftly and provide you with a medical aid.


For Appointment with Dr Raghu: +91 80085 36699
Dr Raghu’s Patient Coordinator: +91 72860 10203
Dr Raghu’s Office Experience: +91 90001 65962
Dr Raghu’s Social Media Communication Channel: +91 97046 51708

Dr. Raghu | Heart Specialist in Hyderabad
Yashoda Hospitals, Raj Bhavan Road, Somajiguda, 1st floor, Room No. 115, Hyderabad -500082, Telangana

Best Cardiologists in Hyderabad


© 2024, Dr. Raghu. All rights reserved. Design & Developed by AMSDigital.in

[gtranslate]
+91-9542475650