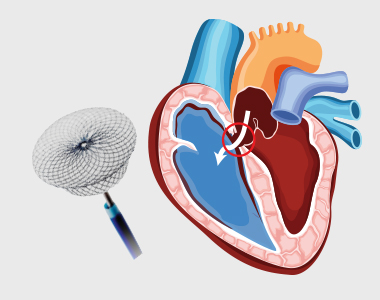
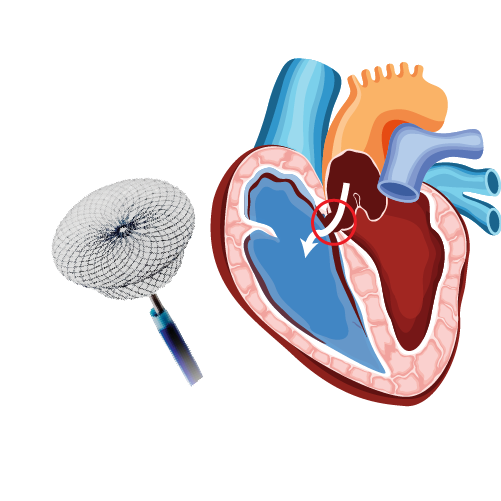
Heart consists of four chambers, of which upper two chambers are called as atria and lower two chambers are called as ventricles. Atrial septal defect (ASD) is a type of congenital heart defect, in which there is an abnormal opening or a hole in interatrial septum (dividing wall between two atria). This opening allows the passage of pulmonary venous blood from left atrium to right atrium, causing mixing of oxygenated and deoxygenated blood in right atrium and increasing the flow of blood to lungs. The increased blood flow may increase the workload of the lungs, and eventually cause damage to heart and lungs.
What causes an ASD?
The exact cause of ASD remains unclear. However, it is believed that during fetal developmental stages, a hole is present in the interatrial septum, which gradually closes before birth or during infancy. If the hole persists, it is called an atrial septal defect.
Types of Atrial Septal Defect or ASD?
Based on the location and development of ASD, it is classified into four types:
Ostium secundum ASD: It occurs in the middle part of the interatrial septum. This is the most common type of ASD and accounts for 75% of all atrial septal defects. This type of ASD is commonly detected in adults in their third and fourth decades of life. Some can be detected in children when an abnormal heart sound is detected at the time of a routine health check or vaccination visit.
Ostium primum ASD (20%): It occurs in the lower part of the interatrial septum, adjacent to atrioventricular (AV) valves. It usually occurs as a part of other congenital heart defects. This defect is usually detected in early life as this is associated with many complications.
Sinus venosis ASD (4%): It occurs in the upper part of the interatrial septum, near the veins that drain into the right and left atrium. This is usually identified in third and fourth decade adults.
Coronary sinus ASD (<1%): It occurs in the interatrial septum between the coronary sinus and the left atrium. This is very uncommon and patients are asymptomatic.
Signs and symptoms
Usually after birth, babies who have ASD may not show any associated signs and symptoms. But, symptoms may appear during adulthood around the age of 30 years. Most of them don’t have any symptoms even after many years.
Some of the common symptoms associated with ASD are:
Heart murmur, a swishing sound that can be heard through a stethoscope
Genetics and environmental factors usually play a role in congenital heart defects. Some conditions during pregnancy may confer high risk for heart defects,
Complications of an untreated ASD:
Right-sided heart failure
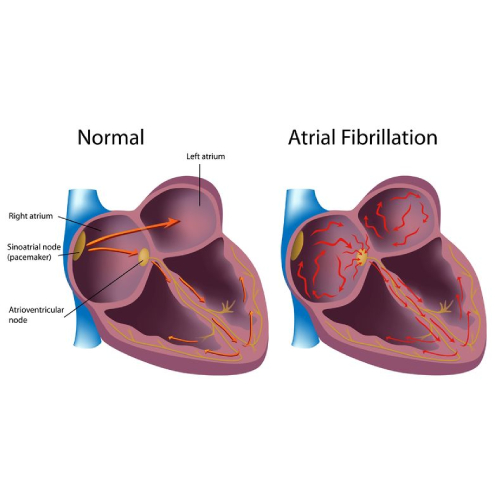
Arrhythmias
Increased risk of a stroke
Shortened life span
Pulmonary hypertension (increased blood flow to the lungs results in increased blood pressure in the lung arteries)
Most ASDs are diagnosed incidentally during regular heath check-ups. If a heart murmur is heard during auscultation, you may be advised to undergo further tests to confirm the diagnosis of ASD:
Echocardiogram: It is a specific diagnostic test for ASD, and provides a detailed image of the heart and blood flow through its chambers. The echocardiogram may show the blood flow through the interatrial septum and the size of defect in the septum.
Chest X-ray: It helps to identify enlarged heart and lung changes.
Electrocardiogram (ECG): It involves recording the electrical activity of the heart, to help identify arrhythmias.
Cardiac catheterization: A thin, flexible tube called catheter is inserted into the blood vessel at the groin or arm and is guided to the heart. This test is helpful to determine the function of heart and its valves, and to measure the blood pressure in the lungs.
Magnetic resonance imaging (MRI): It uses magnetic and radio waves to create three dimensional images of the heart and other organs. This test is recommended if the ASD is not clearly diagnosed with echocardiogram.
Computerized tomography (CT) scan: It uses a series of X-rays to create detailed images of heart; mainly used if echocardiogram doesn’t help to diagnose ASD clearly.
Treatment:
Treatment of ASD depends on the age at diagnosis and the size, location and severity of the defect. Small ASDs might not need any treatment because it closes on its own. The doctor may recommend surgery if the atrial septal defect is large, even with fewer symptoms to prevent problems later in life. Treatment of ASD includes medications and surgery.
Medications usually do not help in closing the hole, but reduces the signs and symptoms associated with ASD and risks of complications after surgery. Drugs such as beta blockers (to maintain regular heartbeat) and anticoagulants (to prevent the formation of blood clots) are used.
Surgery includes cardiac catheterization and open-heart surgery.
Device closure of ASD
In cardiac catheterization, the doctor closes the hole in the septum with a mesh patch or a plug in the defect place using a catheter. The heart tissue then grows around the mesh slowly, sealing the hole permanently. This procedure is mainly performed to repair only the secundum type of atrial septal defects. Defects not amenable to closure with device may need open-heart surgery.
In open-heart surgery, the defect may be closed with stitches or a special patch. This procedure is done under general anesthesia, mainly for repairing primum, sinus venosus and coronary sinus atrial septal defects.
Prevention of ASD:
Atrial septal defects cannot be prevented, but following certain measures during pregnancy might be beneficial to prevent the risk of ASD, such as:
Immunity test for rubella: If the person is not immune to rubella, it is necessary to get vaccinated.
Monitoring current health conditions and medications use: Pre-existing health conditions and usage of any medications should be carefully monitored during pregnancy to prevent the risk of ASD.
Reviewing family medical history: If a person has a family history of congenital defects, it is advised to visit a genetic counsellor before becoming pregnant to know the risks of atrial septal defects.
Coronary artery disease (CAD) is the most common type of heart disease, in which the coronary arteries ( blood vessels that supplies oxygen and nutrients to the heart muscle) become rigid.
Acute myocardial infarction (AMI) is the necrosis of the heart muscles
resulting from acute obstruction of a coronary artery. “Time is Muscle” in AMI .
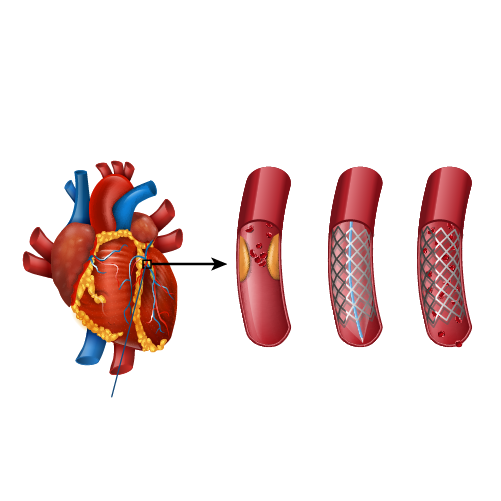
Primary angioplasty is a minimally invasive procedure that uses treats the
obstructed areas of the coronary arteries causing a myocardial infarction
Considering long travel distances and lack of cath lab in many districts – “Lyse now and stent soon” is the apt strategy for managing AMI.
Approach for managing AMI:
Benefits of Primary angioplasty:
Class I therapy for AMI
Preserves heart muscles
Immediate restoration of blood flow
Fast recovery
Saves lives, immediate and long-term benefits
Procedure of primary angioplasty:
A balloon catheter is inserted into the main artery in the groin or arm
The catheter is passed gently into the aorta
The balloon is inflated at the narrowed area(s) of the artery, thereby opening and widening it.
A stent may also be placed to keep the artery open
Acute myocardial infraction is a sudden obstruction in the blood flow to the heart muscle. It is an emergency condition in which the plaque formed due to the deposition of fat, cholesterol, calcium, or cellular waste products is ruptured leading to the formation of thrombus. This leads to the obstruction of the coronary vessels resulting in an acute reduction of blood supply.
Signs and Symptoms:
The symptoms of Acute myocardial infraction include:
Chest Pain- Uninterrupted and intense chest pain often radiates to the neck, shoulder, jaw, and down to the left arm. The chest pain is usually experienced as pressure, squeezing, aching, or burning sensation, and can also be presented as a feeling of indigestion or fullness of gas.
The important signs of the patient to be considered include the following:
Increase in the heart rate
Irregular pulse
Elevated blood pressure
Coughing and wheezing
Nausea and vomiting
Shortening of breath
Distended neck veins
Production of frothy sputum
Excessive sweating, light headedness and palpitations.
Loss of consciousness due to inadequate blood flow to the brain
Causes:
Coronary artery blockage is the primary cause of acute myocardial infarction. It is due to the accumulation of cholesterol in the arteries. The increase in LDL levels (bad cholesterol) in the body leads to plaque formation in the arteries. Saturated and trans fats are other types of fats which also lead to the formation of plaque in the arteries and obstruct the blood flow. Certain dairy products including butter and cheese, meat, beef, and processed foods are the main sources of saturated and trans fats.
During a heart attack, the plaque gets ruptured and spills cholesterol into the bloodstream. This leads to the formation of blood clots, when are big enough can block the artery at the site of rupture and deprives the heart muscle from obtaining enough oxygen and nutrients. There can be a partial block of the artery or a complete block of the artery. A complete block refers to an ST level elevation Myocardial Infraction (STEMI) and a partial block refers to a non-ST elevation Myocardial Infraction (NSTEMI).
Risk Factors:
Some of underlying risk factors of the acute myocardial infraction are modifiable.
Electrocardiogram Electrocardiogram remains a crucial tool used to diagnose a patient with acute myocardial infraction. One of the significant finding is the presence of the raised ST segment.
Cardiac Imaging The coronary cardiac imaging is used to check for the presence or to rule out the coronary artery disease. The test is considered for the individuals who are at risk of having an acute myocardial infraction.
Laboratory procedures:
The laboratory tests should include identification of marker known as cardiac troponins, complete blood picture, lipid profile, renal function and metabolic panel.
Treatment:
Any patient diagnosed with acute myocardial infraction advised to take aspirin 165 mg – 325 mg immediately regardless of their condition (STEMI or NSTEMI). In STEMI the patient should receive dual antiplatelet agents, including heparin infusion. This should immediately be followed by a reperfusion with the percutaneous coronary intervention (PCI). If PCI is unavailable within 90 minutes of diagnosis of STEMI, an intravenous thrombolytic agent should be considered for reperfusion. NSTEMI in a stable asymptomatic patient can be managed with antiplatelet agents.
Prevention:
Any individual can improve heart health and prevent the occurrence of current heart condition by following the below-mentioned lifestyle changes:
Your heart needs to work 24/7 to keep your body systems working. Like any other body tissue, the heart too needs oxygen and nutrients to function efficiently. For this, we have a network of arteries that supply blood to the heart muscles which are called the coronary arteries. There are two chief coronary arteries:
the left and right coronary arteries, that branch out from the aorta near the point where the aorta and the left ventricle meet.
The right coronary artery supplies blood to the right atrium, the right ventricle, a small bottom area of the left ventricle and the back portion of the septum.
The left coronary artery supplies blood to the left atrium and ventricles and the front portion of the septum.
These coronary arteries give out various branches that supply blood to different parts of the heart.
Coronary artery disease:
When there is high level of unhealthy fats in the blood, they gradually start depositing in the insides of the coronary artery vessel wall and form a fatty plaque(atherosclerosis). This gradually narrows the lumen of the coronary arteries which obstructs blood supply to the heart. This condition is called as coronary artery disease. disruption of blood supply to the heart gives rise to a cluster of symptoms, the most important being chest pain or angina.
For continuous circulation, the left and the right side of the heart must work together. Here are the series of steps that causes the blood to flow in the heart, lungs and body.
The right atria receives deoxygenated blood from two large veins- the superior and inferior venacava.
When the atria contracts and the blood passes from the right atrium to the right ventricle through the tricuspid valve.
When the ventricle fills, the tricuspid valve closes.
Next, the ventricle contracts and pushes blood to the pulmonary artery through the pulmonary valve.
The pulmonary artery carries the blood to the lungs where the blood gets oxygenated.
This oxygenated blood enters the left atria of the heart through the pulmonary vein.
Next, the left atria contracts and the blood flows from left atrium into your left ventricle through the open mitral valve.
When the ventricle is full, the mitral valve shuts,
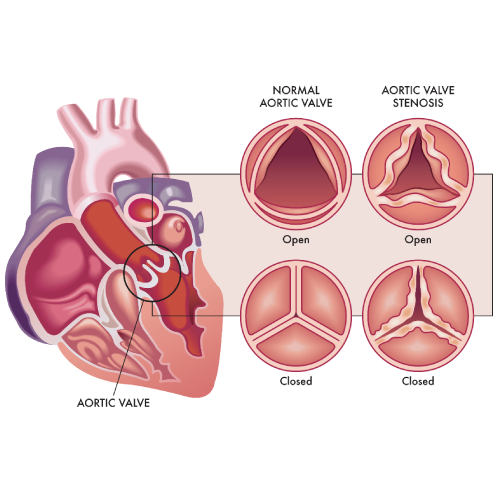
Next, the ventricle contracts and oxygenated blood is passed to the aorta through which it is sent to various parts of the body.